


Executive CI Snapshot
Polycythemia vera is entering a more segmented and mechanism-diverse treatment era as management expands beyond therapeutic phlebotomy and conventional hydroxyurea-based cytoreduction. JAKAFI established targeted JAK1/JAK2 inhibition for adults with an inadequate response to or intolerance of hydroxyurea, while BESREMI introduced long-acting interferon therapy for adults regardless of previous treatment history. Competition is increasingly centred on sustained hematocrit control, reduced phlebotomy dependence, symptom improvement and deeper disease modification.
Commercial momentum is strengthening across the branded PV treatment landscape. Incyte benefits from an established hematology franchise and JAKAFI’s positioning following hydroxyurea failure. JAKAFI XR extends the franchise through a once-daily oral extended-release formulation, improving dosing convenience over twice-daily JAKAFI. PharmaEssentia continues expanding BESREMI adoption through its broad adult indication and long-acting subcutaneous administration. The BESREMI Pen provides a prefilled, adjustable-dose delivery system designed to simplify preparation and self-administration. Future growth will be supported by formulation innovation, convenient routes of administration, earlier treatment initiation, wider reimbursement and increasing demand for durable disease control.
Competitive intensity is expected to increase as differentiated mechanisms advance. Rusfertide represents the most immediate pipeline threat, with its NDA under FDA Priority Review following positive Phase III VERIFY results. Givinostat, sapablursen and bomedemstat provide late-stage competition through HDAC inhibition, TMPRSS6 suppression and LSD1 inhibition. DISC-3405, SLN124 and BEBT-507 expand competition within the hepcidin-regulation pathway, while ZE74-0282 and PRT12396 introduce mutant-selective JAK2V617F inhibition with potential disease-modifying relevance.
Future leadership will require sustained hematocrit control below 45%, durable phlebotomy independence, thrombosis-risk reduction, symptom improvement, molecular response and preservation of normal hematopoiesis. Clear patient selection, compatibility with established therapies, convenient administration, favorable long-term safety and payer-relevant evidence of reduced complications and healthcare utilization will determine specialist adoption, market access and sustained commercial value.
Key Highlights
- Polycythemia vera is a chronic JAK2-driven myeloproliferative neoplasm concentrated primarily among older adults. More than 95% of patients carry a JAK2 variant, supporting molecular diagnosis and targeted therapeutic development.
- The diagnosed PV population was estimated at approximately 88,943 patients in the United States and 126,957 patients across the European Union and United Kingdom in 2025, creating a substantial lifelong treatment population.
- FDA-approved branded treatment is anchored by JAKAFI and BESREMI. JAKAFI targets adults with an inadequate response to or intolerance of hydroxyurea, while BESREMI supports broader adult use regardless of previous treatment history.
- Rusfertide represents the most immediate pipeline threat, with its NDA under FDA Priority Review following Phase III evidence demonstrating improved hematocrit control and reduced therapeutic-phlebotomy requirements.
- Pipeline diversification spans hepcidin mimetics, TMPRSS6-targeted antibodies and RNA therapeutics, HDAC inhibition, LSD1 inhibition and mutant-selective JAK2V617F inhibitors, led by givinostat, sapablursen, bomedemstat, DISC-3405 and SLN124.
- Major unmet needs include persistent phlebotomy dependence, inadequate hematocrit control, thrombosis risk, iron deficiency, symptom burden, treatment intolerance and progression to post-PV myelofibrosis or acute myeloid leukemia.
- Future market leadership will depend on sustained hematocrit control below 45%, phlebotomy independence, thrombosis-risk reduction, molecular response, symptom improvement, convenient administration, favorable long-term safety and compelling payer evidence.
Disease Overview
Polycythemia vera (PV) is a chronic myeloproliferative neoplasm characterized by excessive production of red blood cells, frequently accompanied by elevated white blood cells and platelets. Most patients carry a JAK2 mutation, which drives uncontrolled blood-cell formation. Increased blood viscosity raises the risk of arterial and venous thrombosis, including stroke, heart attack and deep-vein thrombosis. Common symptoms include fatigue, headache, dizziness, pruritus, night sweats and splenomegaly. Diagnosis combines blood counts, JAK2 testing, erythropoietin levels and bone-marrow evaluation. Treatment aims to maintain hematocrit below 45%, prevent thrombosis, control symptoms and reduce progression to myelofibrosis or acute myeloid leukemia.
Epidemiology Analysis
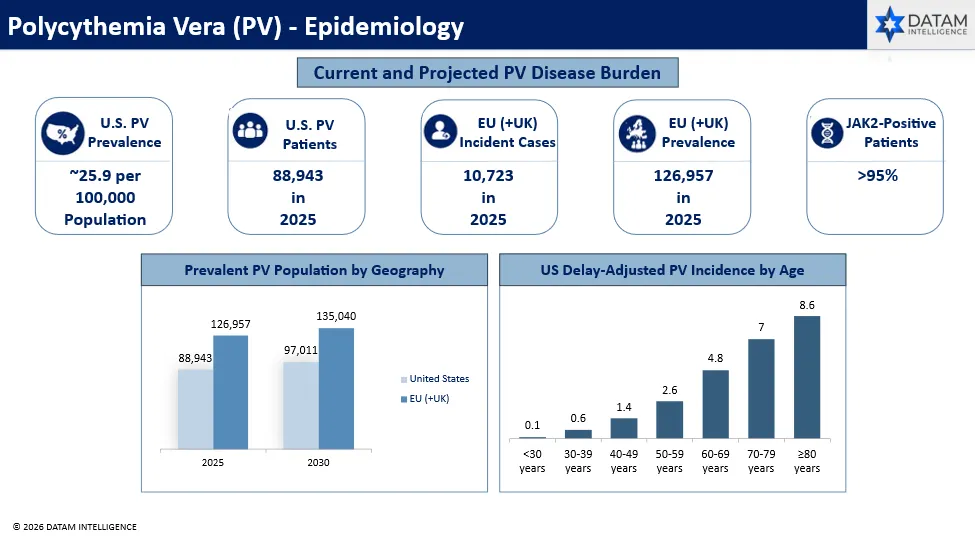
- Polycythemia Vera represents an expanding chronic-disease population. Approximately 88,943 patients were living with PV in the United States in 2025, while the European Union and United Kingdom accounted for 126,957 patients.
- Prevalence is projected to reach 97,011 patients in the United States and 135,040 across the European Union and United Kingdom by 2030, driven primarily by population ageing and prolonged survival rather than an increase in disease incidence.
- Age remains the strongest epidemiological differentiator. Delay-adjusted US incidence rises from 0.1 per 100,000 person-years among individuals younger than 30 to 8.6 among those aged 80 years and older, concentrating diagnosis and treatment demand within older populations.
- Europe generated an estimated 10,723 incident cases in 2025, supporting a steady inflow of patients requiring lifelong monitoring, hematocrit control and thrombosis-risk management.
- More than 95% of patients carry a JAK2 gene variant, enabling molecular confirmation and targeted patient identification. Expanding diagnosed prevalence, long treatment duration and persistent clinical risk strengthen demand for therapies offering durable control, improved tolerability and reduced phlebotomy burden.
Approved Drugs
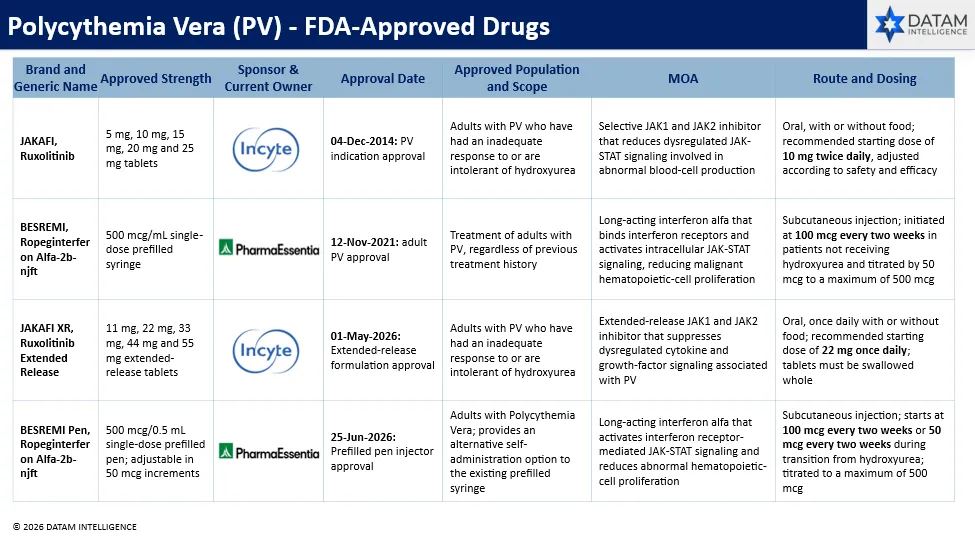
- The FDA-approved Polycythemia Vera treatment landscape is led by ruxolitinib and ropeginterferon alfa-2b-njft, offering targeted Janus kinase inhibition and long-acting interferon therapy for different patient profiles. Recent formulation approvals have expanded treatment convenience while strengthening the commercial positions of Incyte and PharmaEssentia.
- JAKAFI received FDA approval in December 2014 for adults with Polycythemia Vera who have experienced an inadequate response to or are intolerant of hydroxyurea. Ruxolitinib inhibits JAK1 and JAK2 signalling, helping control hematocrit, reduce spleen volume and alleviate disease-related symptoms in eligible patients requiring second-line systemic treatment.
- BESREMi received FDA approval in November 2021 for treating adults with Polycythemia Vera, regardless of previous treatment history. Its broad indication supports use in both treatment-naïve and previously treated patients. The long-acting interferon therapy regulates abnormal blood-cell production and supports sustained control of red blood cells, white blood cells and platelets.
- JAKAFI XR received FDA approval in May 2026 as an extended-release ruxolitinib formulation for adults with an inadequate response to or intolerance of hydroxyurea. Once-daily administration provides greater treatment convenience than twice-daily JAKAFI and may support stronger adherence while extending Incyte’s established ruxolitinib franchise.
- BESREMi Pen received FDA approval in June 2026 as a single-dose prefilled pen injector. Adjustable dosing in 50 mcg increments simplifies preparation and self-administration compared with the existing prefilled syringe, potentially improving treatment consistency and supporting PharmaEssentia’s position in long-term Polycythemia Vera management.
- Competitive differentiation increasingly centres on treatment eligibility, dosing frequency, administration convenience and sustained disease control. BESREMi holds the broadest FDA-approved population while JAKAFI and JAKAFI XR remain positioned following hydroxyurea failure.
FDA New Drug Application Approval Timeline
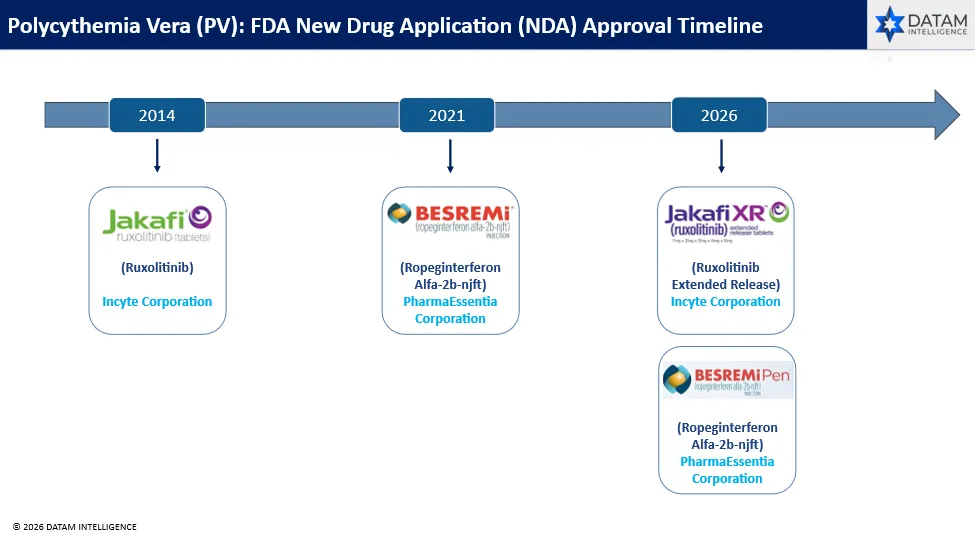
The FDA approval timeline reflects a shift from hydroxyurea-dependent cytoreduction toward targeted pathway inhibition, long-acting interferon therapy and more convenient formulations. Incyte established targeted treatment with JAKAFI in 2014 for adults with an inadequate response to or intolerance of hydroxyurea, introducing JAK1 and JAK2 inhibition into Polycythemia Vera management. BESREMi entered in 2021 as the first FDA-approved interferon specifically indicated for adults with Polycythemia Vera, regardless of previous treatment history, broadening opportunities for earlier systemic intervention. JAKAFI XR gained approval in May 2026, providing once-daily extended-release dosing and improving convenience over the twice-daily formulation. BESREMi Pen followed in June 2026, offering an adjustable prefilled pen designed to simplify self-administration. Collectively, these approvals have shifted competition toward broader treatment eligibility, dosing convenience, adherence and sustained disease control.
Pipeline Analysis
As of July 2026, the therapeutic pipeline for Polycythemia Vera (PV) is robust, encompassing various modalities aimed at slowing disease progression and preserving vision. Here's an overview of key investigational therapies across different classes:
| Company | Asset | Current Stage | Mechanism | Route | Modality |
Takeda / Protagonist Therapeutics | Rusfertide (PTG-300 / TAK-121) | NDA Priority Review | Hepcidin mimetic that restricts iron availability for erythropoiesis and controls excess red-blood-cell production | Subcutaneous | Synthetic peptide |
| Italfarmaco | Givinostat | Phase III | Pan-HDAC inhibitor designed to suppress abnormal JAK2-driven transcription and malignant hematopoietic-cell proliferation | Oral | Small molecule |
Ono Pharmaceutical / Ionis Pharmaceuticals | Sapablursen | Phase III | TMPRSS6-targeting antisense therapy that increases endogenous hepcidin and reduces iron availability for erythropoiesis | Subcutaneous | Antisense oligonucleotide |
| Merck & Co. | Bomedemstat (MK-3543 / IMG-7289) | Phase II/III | LSD1 inhibitor designed to modify abnormal hematopoietic stem-cell differentiation and malignant clone activity | Oral | Small molecule |
| Disc Medicine | DISC-3405 | Phase II | Anti-TMPRSS6 antibody designed to increase hepcidin and reduce iron availability for red-blood-cell production | Parenteral | Monoclonal antibody |
Chengdu Zenitar Biomedical | Flonoltinib Maleate | Phase II | JAK-family inhibitor intended to suppress dysregulated JAK-STAT signalling in PV | Oral | Small molecule |
| Kartos Therapeutics | Navtemadlin (KRT-232) | Phase II | MDM2 inhibitor that restores p53-mediated apoptosis in malignant hematopoietic cells | Oral | Small molecule |
| Silence Therapeutics | SLN124 | Phase I/II | TMPRSS6-targeting siRNA designed to increase endogenous hepcidin and restrict iron-driven erythropoiesis | Subcutaneous | siRNA |
| Mabwell | 9MW3011 | Phase I | Anti-TMPRSS6 antibody designed to increase hepcidin and regulate iron availability | Intravenous | Monoclonal antibody |
| BeBetter Med | BEBT-507 | Phase I | GalNAc-conjugated siRNA targeting TMPRSS6 to increase hepcidin and control erythrocytosis | Subcutaneous | siRNA |
| Eilean Therapeutics | ZE74-0282 | Phase I | Mutant-selective JAK2V617F inhibitor designed to preserve wild-type JAK2 signalling | Oral | Small molecule |
| Prelude Therapeutics | PRT12396 | Phase I | Mutant-selective JAK2V617F JH2-domain inhibitor intended to suppress mutant hematopoietic clones | Oral | Small molecule |
Hangzhou GluBio Pharmaceutical | GLB-001 | Phase I | CK1α-targeting molecular-glue degrader designed to induce degradation of disease-associated proteins | Oral | Small-molecule protein degrader |
* LIST NOT EXHAUSTIVE
Market Size & Forecasting
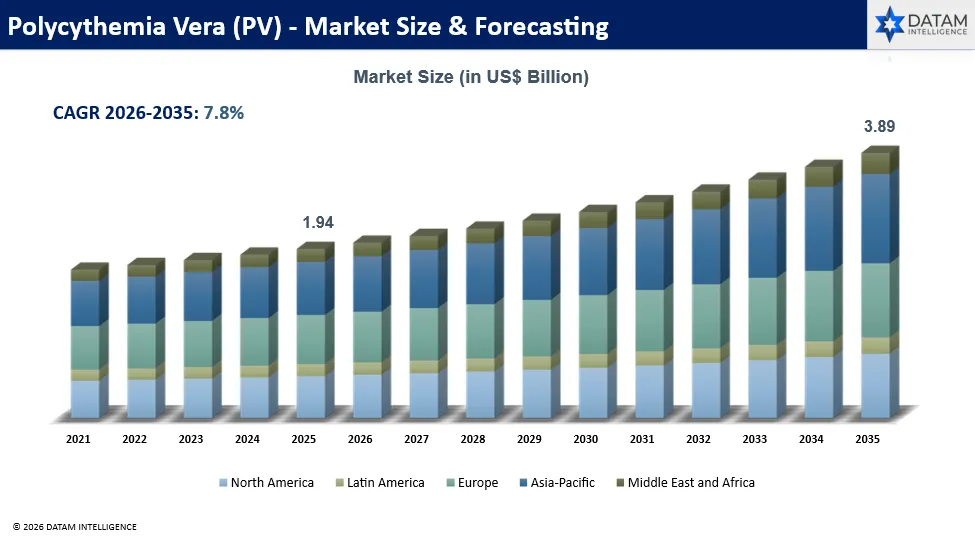
The global polycythemia vera (PV) market stood at US$ 1.94 billion in 2025 and is expected to reach US$ 3.89 billion by 2035, growing with a CAGR of 7.8% during the forecast period 2026-2035.
Competitive Landscape and Market Positioning
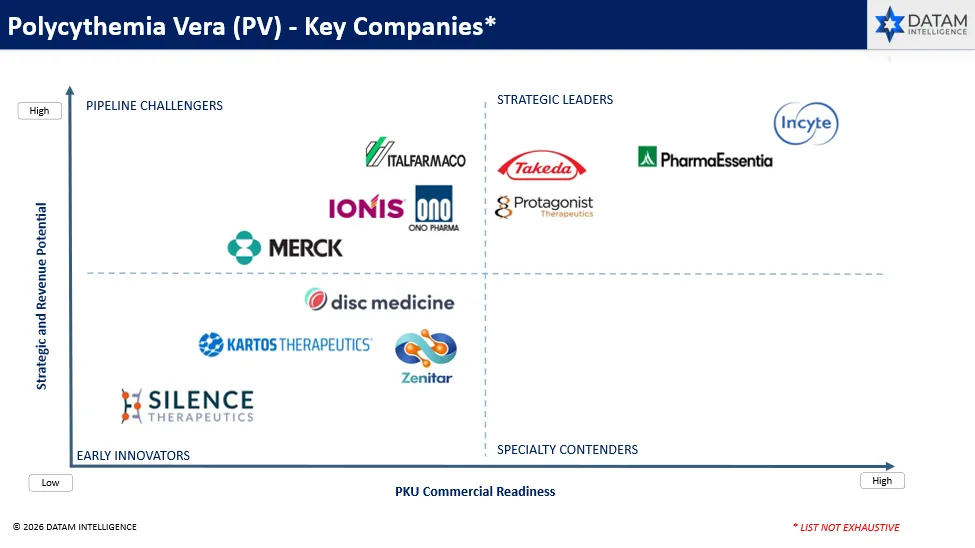
- The PV market is transitioning from conventional hematocrit control through phlebotomy and hydroxyurea toward targeted JAK inhibition, long-acting interferon therapy, iron-restriction mechanisms and potentially disease-modifying approaches directed at malignant hematopoietic clones.
- Incyte and PharmaEssentia hold the leading FDA-approved positions through JAKAFI and BESREMI. Incyte benefits from an established presence among patients resistant or intolerant to hydroxyurea, while BESREMI provides a long-acting interferon option for adults regardless of previous treatment history.
- Takeda and Protagonist are approaching commercialization with rusfertide, a first-in-class hepcidin mimetic under FDA Priority Review. Strong Phase III hematocrit-control and phlebotomy-reduction results position rusfertide as the most immediate competitive threat to existing therapies, particularly as an add-on treatment for phlebotomy-dependent patients.
- Italfarmaco, Ono/Ionis and Merck are advancing differentiated late-stage programs. Givinostat targets abnormal hematopoietic proliferation through HDAC inhibition, sapablursen increases endogenous hepcidin through TMPRSS6 suppression and bomedemstat employs LSD1 inhibition to pursue deeper disease modification.
- Disc Medicine, Silence Therapeutics, Chengdu Zenitar and Kartos Therapeutics represent emerging or watchlist competitors. Their antibody, siRNA, JAK-pathway and MDM2-targeted approaches broaden mechanistic competition but require further clinical validation, regulatory clarity and evidence of sustained corporate commitment.
- Future market leadership will depend on durable hematocrit control, reduced phlebotomy dependence, prevention of thrombosis, symptom improvement, molecular-response depth and favorable long-term safety. Companies demonstrating meaningful disease modification alongside convenient administration and compatibility with existing standard-of-care therapies will be best positioned to capture future PV treatment share.
Target Opportunity Profile (TOP)
To compete effectively in polycythemia vera, emerging therapies must deliver sustained hematocrit control below 45%, reduce or eliminate therapeutic phlebotomy and improve disease-related symptoms without causing clinically significant cytopenias. Competitive success will require efficacy across low- and high-risk patients, including those inadequately controlled by or intolerant to hydroxyurea, interferon or ruxolitinib. Differentiation should be demonstrated through thrombosis-risk reduction, molecular response, convenient administration, durable disease control and credible long-term safety evidence.
Target Opportunity Profile (TOP) - Competitive Attributes
| Dimension | Desired Profile for Emerging PKU Therapies | Strategic Rationale |
| Safety |
| PV requires lifelong treatment; predictable safety and limited myelosuppression are essential for sustained use. |
| Efficacy |
| Hematocrit control and phlebotomy independence are the primary near-term benchmarks; thrombosis prevention provides stronger clinical differentiation. |
| Mechanism of Action |
| Mechanistic selectivity could improve disease control while avoiding the cytopenias associated with broader marrow suppression. |
| Route of Administration |
| Convenient delivery can improve adherence and differentiate new therapies from burdensome phlebotomy and clinic-administered treatment. |
| Dosing Frequency |
| Lower treatment burden supports persistence, particularly in a chronic disease requiring long-term management. |
| Modality |
| Multiple modalities create opportunities to differentiate through selectivity, dosing durability and depth of disease control. |
| Durability |
| Durable control is critical for reducing cumulative thrombotic risk and demonstrating value beyond short-term blood-count normalization. |
| Innovation Level |
| Precision targeting and molecular-response evidence could overcome the primarily symptom- and count-directed limitations of existing therapies. |
| Clinical Impact |
| Clinicians and payers increasingly require patient-relevant outcomes beyond hematologic response alone. |
| Patient-Population Targeting |
| Broad eligibility expands commercial opportunity, while biomarker- or treatment-history-based positioning supports focused adoption. |
| Treatment Positioning |
| Flexible positioning can support adoption across different risk categories, treatment histories and physician preferences. |
| Commercial Differentiation |
| Market uptake will depend on clinically meaningful differentiation, reimbursement evidence and integration into established hematology practice. |
Unmet Needs & Market Dynamics
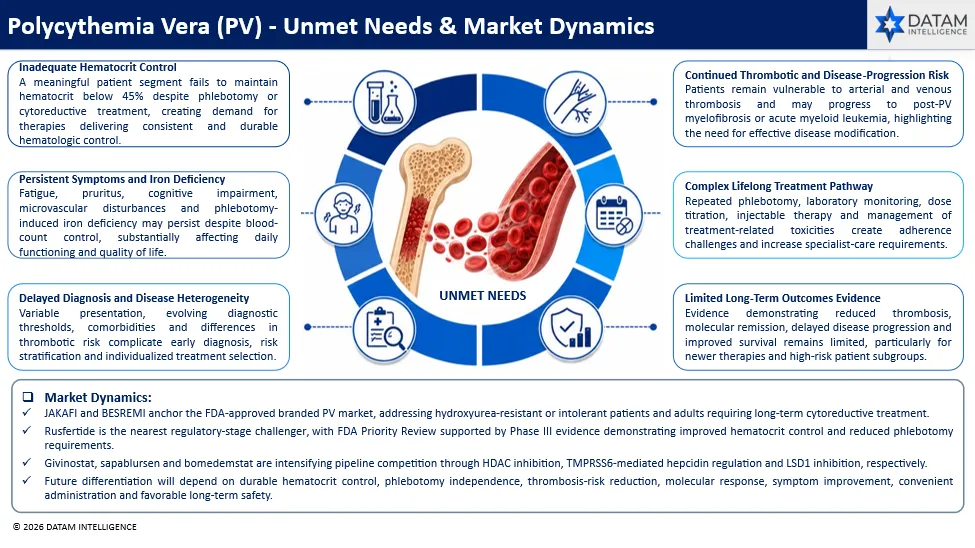
Polycythemia vera presents substantial unmet need because phlebotomy and available cytoreductive therapies do not consistently provide durable hematocrit control, eliminate thrombotic risk or prevent disease progression. Many patients experience persistent erythrocytosis, fatigue, pruritus, cognitive impairment and phlebotomy-induced iron deficiency. Responses to hydroxyurea, interferon and ruxolitinib vary, while cytopenias, tolerability concerns, injectable administration, repeated laboratory monitoring and specialist-care requirements may reduce long-term treatment persistence.
The treatment landscape is evolving toward earlier risk-adapted intervention, sustained hematocrit control below 45%, reduced phlebotomy dependence and therapies targeting underlying disease biology. Emerging approaches include hepcidin mimetics, TMPRSS6-targeted antibodies and RNA therapeutics, HDAC inhibition, LSD1 inhibition and mutant-selective JAK2V617F inhibitors. Rusfertide represents the nearest regulatory-stage challenger, while givinostat, sapablursen and bomedemstat are strengthening late-stage competition. Future differentiation will depend on durable hematologic control, thrombosis-risk reduction, molecular response, symptom improvement, convenient administration and favorable long-term safety. Evidence demonstrating delayed progression to post-PV myelofibrosis or acute myeloid leukemia will provide the strongest basis for meaningful disease-modification claims.
Strategic Summary
- The PV competitive landscape is shifting from a treatment pathway centered on phlebotomy and hydroxyurea toward a segmented market encompassing JAK inhibition, long-acting interferon therapy, hepcidin-pathway modulation, epigenetic intervention and mutant-selective JAK2 targeting. JAKAFI and BESREMI anchor FDA-approved branded management, while regulatory-stage rusfertide raises the near-term benchmark for sustained hematocrit control and phlebotomy reduction.
- Maintaining hematocrit below 45% will remain a core clinical requirement, but hematologic control alone is unlikely to provide durable differentiation. Competitive advantage will increasingly require reduced thrombosis risk, sustained phlebotomy independence, improved fatigue and pruritus, preservation of normal blood-cell production and meaningful reductions in JAK2V617F allele burden.
- Pipeline competition is broadening across hepcidin mimetics, TMPRSS6-targeted antibodies and RNA therapeutics, HDAC inhibition, LSD1 inhibition and mutant-selective JAK2V617F inhibitors. Rusfertide represents the most immediate pipeline threat, while givinostat, sapablursen and bomedemstat provide differentiated late-stage mechanisms. DISC-3405, SLN124, BEBT-507, ZE74-0282 and PRT12396 offer longer-term potential but require stronger clinical validation.
- Commercial success will depend on an integrated value proposition combining durable hematocrit control, reduced phlebotomy burden, convenient administration, favorable long-term safety and measurable improvement in daily functioning. Clear positioning across low- and high-risk patients, compatibility with existing cytoreductive treatment and evidence of reduced thrombosis, progression and healthcare utilization will be central to hematologist adoption, payer acceptance and sustained market access.
Why Buy Our Polycythemia Vera (PV) Competitive Intelligence Report?
The PV market is entering a more competitive and mechanism-diverse treatment era, driven by the established positions of JAKAFI and BESREMI, regulatory advancement of rusfertide and growing investment in hepcidin modulation, TMPRSS6 targeting, HDAC inhibition, LSD1 inhibition and mutant-selective JAK2 therapies. Companies require clear intelligence on hematocrit control, phlebotomy reduction, thrombosis risk, molecular response, symptom improvement, safety, regulatory progress and pipeline disruption. Our report translates the evolving PV landscape into actionable clinical, commercial and investment strategies.
Identify Where Competition Is Intensifying
Understand how JAKAFI and BESREMI define the current branded market, how rusfertide could reshape phlebotomy-dependent treatment and which late-stage and emerging mechanisms may drive the next competitive wave.
Prioritize the Right Patient Segments
Assess commercially relevant populations, including low- and high-risk patients, phlebotomy-dependent patients, individuals resistant or intolerant to hydroxyurea and patients inadequately controlled with interferon or ruxolitinib.
Evaluate Asset Differentiation
Compare therapies based on hematocrit control, phlebotomy independence, blood-count normalization, symptom improvement, molecular response, thrombosis prevention, administration convenience and long-term safety.
Track Regulatory and Launch Readiness
Monitor pivotal-trial progress, clinical readouts, FDA milestones, regulatory submissions, geographic expansion, manufacturing readiness and commercialization timelines across approved and investigational therapies.
Support Pricing and Access Planning
Understand payer expectations, reimbursement barriers, treatment eligibility, monitoring requirements and evidence thresholds influencing hematologist adoption across major markets.
Strengthen Business Development Decisions
Identify licensing, partnership, acquisition and investment opportunities across hepcidin mimetics, TMPRSS6-targeted antibodies and RNA therapies, HDAC and LSD1 inhibitors, mutant-selective JAK2 inhibitors and next-generation disease-modifying platforms.
