


Executive CI Snapshot
Myelofibrosis (MF) is entering a more differentiated competitive phase as treatment development moves beyond conventional JAK-pathway suppression toward phenotype-directed combinations and therapies targeting distinct disease biology. The current U.S. commercial landscape includes Jakafi/Jakafi XR (ruxolitinib), Inrebic (fedratinib), Vonjo (pacritinib) and ojjaara (momelotinib). These therapies have progressively broadened treatment options across intermediate- and high-risk MF, anemia-associated disease and severe thrombocytopenia. The May 2026 approval of once-daily Jakafi XR further strengthened the ruxolitinib franchise through formulation-based lifecycle expansion.
Competitive leadership is concentrated among Incyte, GSK, Sobi and Bristol Myers Squibb, each supported by an FDA-approved MF franchise. Incyte retains a strong incumbent position through ruxolitinib, while GSK differentiates Ojjaara around MF-associated anemia and Sobi positions Vonjo specifically for patients with platelet counts below 50 × 10⁹/L. Bristol Myers Squibb maintains an established JAK2-directed option through Inrebic. Novartis represents an important additional strategic competitor rather than an FDA-approved U.S. MF franchise owner, with pelabresib currently in Phase 3 development in combination with ruxolitinib.
The next competitive wave is becoming substantially more mechanism-diverse. Karyopharm's selinexor plus ruxolitinib has completed pivotal Phase 3 SENTRY evaluation, with the company announcing plans for an accelerated-approval sNDA submission in August 2026. Geron's imetelstat remains in pivotal Phase 3 development for JAK-inhibitor relapsed/refractory MF, while navtemadlin is advancing through the Phase 3 POIESIS trial targeting MDM2–p53 biology in patients with suboptimal response to ruxolitinib. Novartis is advancing the BET inhibitor pelabresib, while Takeda is developing the activin-pathway agent elritercept for MF-associated anemia.
From a CI perspective, future leadership is unlikely to be determined by spleen-volume reduction alone. Competitive differentiation is increasingly shifting toward simultaneous control of splenomegaly and constitutional symptoms, improvement in anemia and transfusion burden, applicability in thrombocytopenic patients, durable efficacy after JAK-inhibitor exposure and tolerable long-term hematologic safety. The highest strategic value could ultimately accrue to therapies capable of demonstrating credible disease modification through deeper control of the malignant clone, improvement in marrow biology or meaningful effects on progression and survival. As combination and non-JAK strategies mature, treatment sequencing is likely to become increasingly phenotype- and disease-stage-specific rather than dominated by a single JAK-inhibitor paradigm.
Key Highlights
- Myelofibrosis remains a rare and clinically heterogeneous hematologic malignancy, with U.S. prevalence estimated at 6.3 per 100,000 population and incidence at 1.56 per 100,000 person-years. Approximately 70% of patients are cytopenic at diagnosis, highlighting the major clinical burden associated with anemia and thrombocytopenia.
- The FDA-approved treatment landscape is led by Jakafi/Jakafi XR, Inrebic, Vonjo and Ojjaara, with therapeutic differentiation increasingly centered on anemia status, platelet count, disease risk, prior JAK inhibitor exposure and dosing convenience.
- Incyte, GSK, Sobi and Bristol Myers Squibb hold leading commercial positions through FDA-approved myelofibrosis therapies, while Novartis maintains a strong strategic position through its established global MF presence and the Phase 3 development of pelabresib with ruxolitinib.
- The therapeutic pipeline is becoming increasingly mechanism-diverse, with late-stage development spanning XPO1 inhibition, MDM2 targeting, telomerase inhibition, BET inhibition and activin-pathway modulation. Key programs include selinexor plus ruxolitinib, navtemadlin plus ruxolitinib, pelabresib plus ruxolitinib, imetelstat and elritercept.
- The report estimates the global myelofibrosis market at US$1.7 billion in 2025, reaching US$3.48 billion by 2035 at a 7.6% CAGR during 2026-2035. Future competitive leadership is expected to depend on durable spleen and symptom control, improvement in cytopenias and transfusion dependence, post-JAK efficacy, favorable hematologic safety and credible evidence of disease modification.
Disease Overview
Myelofibrosis is a chronic, clonal myeloid malignancy within the Philadelphia chromosome-negative myeloproliferative neoplasms, characterized by ineffective hematopoiesis, progressive bone marrow fibrosis, extramedullary hematopoiesis, and a variable risk of leukemic transformation. It may arise de novo as primary myelofibrosis or evolve from polycythemia vera or essential thrombocythemia. The disease originates from an abnormal hematopoietic stem-cell clone, with constitutive activation of the JAK-STAT signaling pathway driven most commonly by JAK2, CALR, or MPL mutations. Abnormal megakaryocytes and other clonal cells release inflammatory and profibrotic mediators that remodel the bone-marrow microenvironment, promoting reticulin and collagen deposition and progressively impairing normal blood-cell production.
Clinically, myelofibrosis is highly heterogeneous. Patients may develop anemia, thrombocytopenia, or leukocyte abnormalities, leukoerythroblastosis, constitutional symptoms, and marked splenomegaly caused largely by extramedullary hematopoiesis. Fatigue, weight loss, night sweats, fever, bone pain, abdominal discomfort, and early satiety can substantially impair quality of life. Disease progression may result in transfusion dependence, severe cytopenias, marrow failure, or transformation to acute myeloid leukemia. Prognosis is determined by clinical, cytogenetic, and molecular features. Treatment is risk- and symptom-adapted, with JAK inhibitors central to disease management, while allogeneic hematopoietic stem-cell transplantation remains the only potentially curative treatment.
Epidemiology Analysis
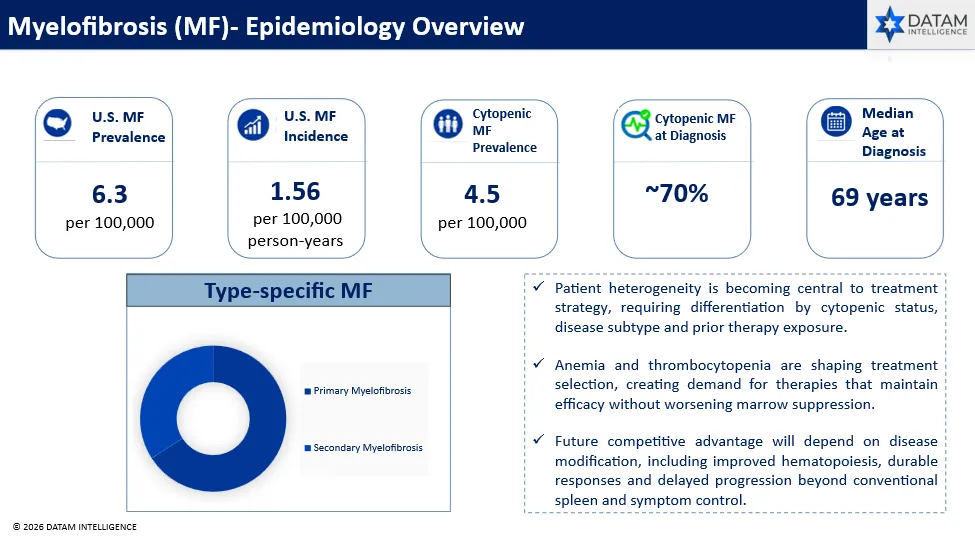
Myelofibrosis is a rare hematologic malignancy with a clinically significant disease burden, particularly among older adults and patients presenting with cytopenias. Recent U.S. epidemiologic evidence estimates an overall myelofibrosis prevalence of 6.3 per 100,000 population and an incidence of 1.56 per 100,000 person-years, highlighting the relatively small but clearly defined patient population. Cytopenic myelofibrosis represents an important component of the disease burden, with an estimated prevalence of 4.5 per 100,000 population. Approximately 70% of patients are cytopenic at diagnosis, emphasizing the substantial contribution of anemia and thrombocytopenia to clinical presentation and treatment complexity.
The disease predominantly affects older adults, with a median age at diagnosis of approximately 69 years, creating additional challenges related to comorbidities, treatment tolerance and long-term disease management. Epidemiologically, myelofibrosis can be classified into primary myelofibrosis and secondary myelofibrosis, with the latter developing following progression of underlying myeloproliferative neoplasms such as polycythemia vera or essential thrombocythemia. Overall, the epidemiologic profile underscores a heterogeneous patient population in which cytopenic burden, advanced age and disease subtype strongly influence clinical management, treatment selection and the need for therapies capable of providing durable disease control without further compromising hematopoiesis.
Approved Drugs
The FDA-approved treatment landscape for myelofibrosis (MF) has evolved substantially over the past decade, moving from a single JAK inhibitor option toward a more differentiated, biology-driven therapeutic framework. Current approved therapies primarily target dysregulated JAK–STAT signaling, with newer agents extending activity toward pathways such as ACVR1 and IRAK1 to address distinct clinical phenotypes including anemia and severe thrombocytopenia. Established therapies such as JAKAFI (ruxolitinib) and INREBIC (fedratinib) are complemented by newer approvals including VONJO (pacritinib), OJJAARA (momelotinib) and the extended-release formulation JAKAFI XR. This expanding treatment landscape has enabled more tailored therapy according to platelet count, anemia status, prior JAK inhibitor exposure and overall disease risk. The growing differentiation among approved agents is increasingly shaping treatment sequencing, patient selection and competitive positioning across the myelofibrosis therapeutic landscape.
| Brand and Generic Name | Sponsor | Current Owner | Approval Date | MOA |
| Jakafi XR (Ruxolitinib) | Incyte Corporation | Incyte Corporation | May, 2026 | JAK1 and JAK2 inhibitor; suppresses dysregulated JAK-STAT signaling |
| Ojjaara (Momelotinib) | GlaxoSmithKline LLC | GSK plc | September, 2023 | JAK1/JAK2 and ACVR1 inhibitor; ACVR1 inhibition reduces hepcidin and increases iron availability for erythropoiesis |
| Vonjo (Pacritinib) | CTI BioPharma Corp. | Swedish Orphan Biovitrum AB (Sobi) | February, 2022 | JAK2, IRAK1 and ACVR1 inhibitor; also inhibits FLT3 while sparing JAK1 at clinically relevant concentrations |
| Inrebic (Fedratinib) | Impact Biomedicines, Inc. | Bristol Myers Squibb | August, 2019 | Selective JAK2 inhibitor; inhibits wild-type and mutationally activated JAK2 and downstream STAT signaling |
| Jakafi (Ruxolitinib) | Incyte Corporation | Incyte Corporation | November, 2011 | JAK1 and JAK2 inhibitor; inhibits cytokine-mediated JAK-STAT signaling |
Competitive Timeline: Approvals
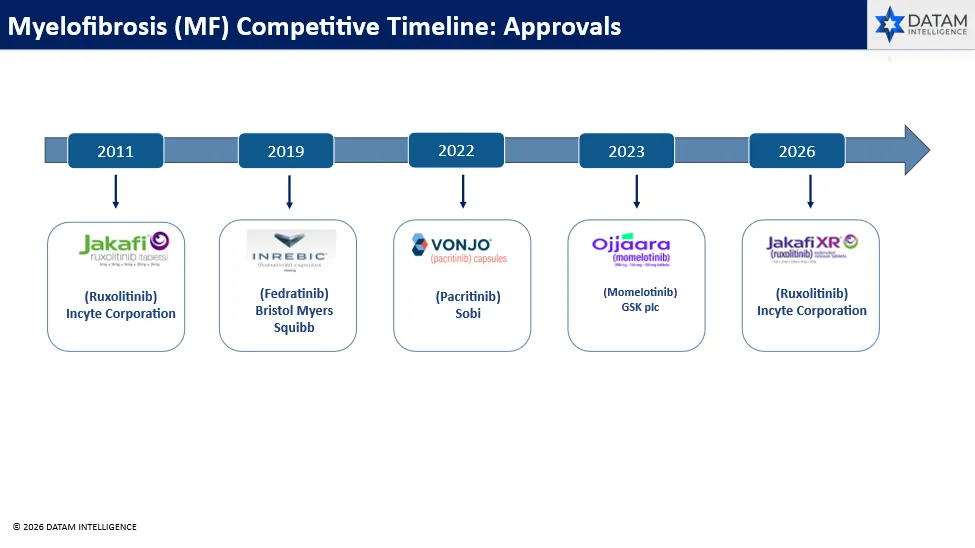
The myelofibrosis approval timeline highlights a progressive evolution within JAK pathway-directed therapy, with increasing differentiation around cytopenias, anemia and dosing convenience. JAKAFI (ruxolitinib) established the first targeted treatment benchmark in 2011, followed by INREBIC (fedratinib) in 2019. The landscape broadened further with VONJO (pacritinib) in 2022 for patients with severe thrombocytopenia and OJJAARA (momelotinib) in 2023 for patients with anemia, extending treatment beyond spleen and symptom control toward clinically defined disease phenotypes. The 2026 approval of JAKAFI XR added a once-daily extended-release option for ruxolitinib therapy. Overall, the competitive landscape remains centered on JAK–STAT inhibition, with differentiation increasingly driven by platelet eligibility, anemia benefit, prior JAK inhibitor exposure, dosing convenience, symptom control and the ability to address distinct myelofibrosis phenotypes.
Pipeline Analysis
As of August 2026, the myelofibrosis therapeutic pipeline is increasingly focused on disease biology beyond JAK inhibition. Investigational strategies target JAK–STAT signaling, p53 regulation, telomerase, BET and LSD1 epigenetic pathways, PIM kinases, inflammatory cytokines and ineffective erythropoiesis. Combination approaches with JAK inhibitors are also being developed to improve spleen response, anemia and symptom control. Overall, the pipeline is shifting toward mechanism-driven and potentially disease-modifying therapies aimed at suppressing malignant clones, modulating marrow fibrosis and improving hematopoiesis:
| Sponsor | Intervention | Clinical Stage | MoA | RoA | Modality | |||
Karyopharm Therapeutics Inc. | Selinexor + Ruxolitinib | Phase 3 | XPO1 inhibition combined with JAK1/JAK2 inhibition | Oral | Small Molecule Combination | |||
| Kartos Therapeutics, Inc. | Navtemadlin + Ruxolitinib | Phase 3 | MDM2 inhibition restores p53 activity combined with JAK1/JAK2 inhibition | Oral | Small Molecule Combination | |||
| Novartis Pharmaceuticals | Pelabresib + Ruxolitinib | Phase 3 | BET protein inhibition combined with JAK1/JAK2 inhibition | Oral | Small Molecule Combination | |||
| Geron Corporation | Imetelstat | Phase 3 | Direct telomerase inhibition targeting malignant hematopoietic clones | Intravenous | Oligonucleotide Therapeutic | |||
Chengdu Zenitar Biomedical Technology Co., Ltd. | Flonoltinib + Ruxolitinib | Phase 3 | Kinase pathway inhibition combined with JAK1/JAK2 inhibition | Oral | Small Molecule Combination | |||
| PharmaEssentia Corporation | Ropeginterferon Alfa-2b | Phase 3 | Interferon receptor activation suppressing malignant myeloproliferative signaling | Subcutaneous | Recombinant Protein | |||
Takeda Pharmaceutical Company Limited | Elritercept | Phase 3 | Activin receptor type IIA ligand trapping to promote erythropoiesis | Subcutaneous | Fusion Protein | |||
| Bristol Myers Squibb | Luspatercept | Phase 3 | TGF-β superfamily ligand trapping to enhance erythroid maturation | Subcutaneous | Fusion Protein | |||
Sumitomo Pharma America, Inc. | Nuvisertib (TP-3654) | Phase1/2 | Selective PIM1 kinase inhibition targeting malignant signaling and fibrosis | Oral | Small Molecule | |||
University of Hong Kong / Merck & Co., Inc. | Bomedemstat + Ruxolitinib | Phase 2 | LSD1 inhibition combined with JAK1/JAK2 inhibition | Oral | Small Molecule Combination | |||
Icahn School of Medicine at Mount Sinai / Dompé | Reparixin | Phase 2 | CXCR1/CXCR2 inhibition reducing inflammatory signaling | Oral | Small Molecule | |||
Icahn School of Medicine at Mount Sinai / Novartis | Canakinumab | Phase 2 | IL-1β neutralization reducing inflammatory cytokine signaling | Subcutaneous | Monoclonal Antibody | |||
Ajax Therapeutics / Eli Lilly and Company | AJ1-11095 | Phase 1 | Type II JAK2 inhibition targeting mutant and activated JAK2 signaling | Oral | Small Molecule | |||
| Telios Pharma, Inc. | TL-895 + Ruxolitinib | Phase 1/2 | BTK pathway inhibition combined with JAK1/JAK2 inhibition | Oral | Small Molecule Combination | |||
| iOnctura SA | Roginolisib + Ruxolitinib | Phase 1/2 | PI3Kδ inhibition combined with JAK1/JAK2 inhibition | Oral | Small Molecule Combination | |||
HOVON / Active Biotech AB | Tasquinimod ± Ruxolitinib | Phase 1/2 | S100A9-directed immunomodulation targeting the inflammatory marrow microenvironment | Oral | Small Molecule | |||
Chia Tai Tianqing Pharmaceutical Group Co., Ltd. | TQ05105 + TQB3617 | Phase 1/2 | Targeted kinase pathway inhibition suppressing abnormal myeloproliferative signaling | Oral | Small Molecule Combination | |||
Suzhou Junjing BioSciences Co., Ltd. | WJ01024 + Ruxolitinib | Phase 1/2 | Targeted pathway inhibition combined with JAK1/JAK2 blockade | Oral | Small Molecule Combination | |||
University of Kansas Medical Center / Menarini Group / Sobi | Tagraxofusp + Pacritinib | Early Phase 1 | CD123-targeted cytotoxic activity combined with JAK2/IRAK1 inhibition | Intravenous + Oral | Fusion Protein + Small Molecule | |||
Market Size & Forecasting
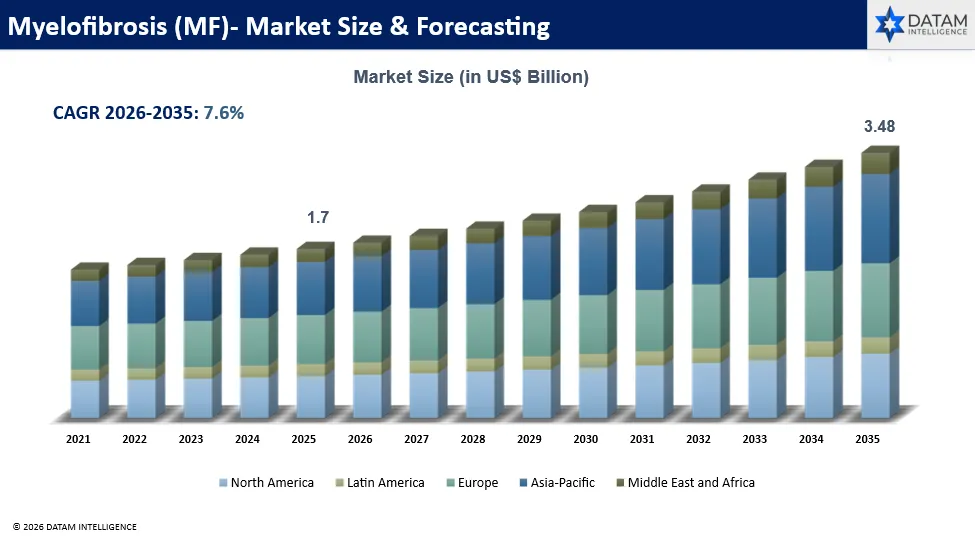
The global myelofibrosis (MF) market stood at US$1.7billion in 2025 and is expected to reach US$3.48 billion by 2035, growing with a CAGR of 7.6% during the forecast period 2026-2035.
Competitive Landscape and Market Positioning
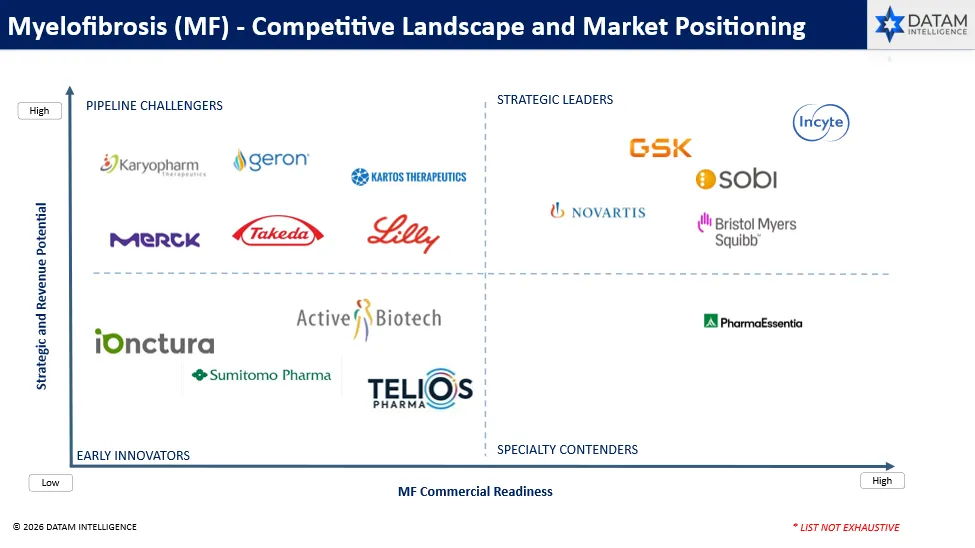
The myelofibrosis competitive landscape is increasingly differentiated by regulatory maturity, commercial presence, pipeline advancement and the ability to address persistent unmet needs such as anemia, thrombocytopenia, post-JAK inhibitor failure and disease modification. Incyte, GSK, Sobi and Bristol Myers Squibb occupy the Strategic Leaders quadrant based on their FDA-approved myelofibrosis therapies, established hematology franchises and high commercial readiness. Novartis is also positioned among the Strategic Leaders due to its established global myelofibrosis presence and the advancement of pelabresib into Phase 3 development, providing additional late-stage pipeline depth.
The Pipeline Challengers quadrant includes Karyopharm Therapeutics, Geron, Kartos Therapeutics, Merck, Takeda and Eli Lilly, reflecting differentiated investigational mechanisms and advancing clinical programs but lower current MF commercial readiness compared with approved competitors. iOnctura, Active Biotech, Sumitomo Pharma and Telios Pharma remain Early Innovators with earlier-stage assets and emerging biological approaches. PharmaEssentia is positioned as a Specialty Contender, supported by an established myeloproliferative-neoplasm platform and advancing MF development. Overall, competition is shifting beyond conventional JAK inhibition toward deeper disease control, cytopenia improvement, post-JAK efficacy and potential disease modification.
Target Opportunity Profile (TOP)
To compete effectively against established myelofibrosis therapies such as Jakafi, Jakafi XR, Inrebic, Vonjo and Ojjaara, emerging therapies must demonstrate a superior Target Opportunity Profile across several critical dimensions. Competitive differentiation will increasingly depend on achieving deeper and more durable spleen and symptom responses, meaningful improvement in anemia and transfusion dependence, activity in thrombocytopenic and post-JAK inhibitor populations, favorable long-term tolerability and reduced treatment-related myelosuppression. Greater value will also come from therapies that demonstrate evidence of disease modification, including reduction in marrow fibrosis, suppression of malignant clones, improved hematopoiesis and delayed progression or leukemic transformation, while maintaining convenient oral or less burdensome dosing.
Target Opportunity Profile (TOP) - Competitive Attributes
| Dimension | Desired Profile for Emerging Therapies | Rationale |
| Safety |
| Myelofibrosis patients frequently have baseline cytopenias and substantial comorbidity burden. A differentiated therapy should avoid worsening marrow suppression while supporting prolonged treatment. |
| Efficacy |
| Spleen-volume reduction and symptom improvement remain core regulatory and clinical efficacy benchmarks. Emerging therapies must demonstrate benefit beyond established JAK inhibitor performance. |
| Disease Modification |
| Current JAK inhibitors primarily control spleen and constitutional symptoms. Demonstrating biological modification of the underlying malignant clone represents a major competitive opportunity. |
| Anemia Benefit |
| Anemia is a major determinant of morbidity, prognosis and treatment selection in MF. Therapies capable of simultaneously controlling disease and improving erythropoiesis would have strong clinical differentiation. |
| Thrombocytopenia Profile |
| Severe thrombocytopenia restricts use of several MF therapies and represents a high-unmet-need population. Broad platelet-count eligibility could materially expand addressable patients. |
| Survival and Progression |
| Survival benefit remains one of the strongest potential differentiators, particularly in intermediate-2/high-risk and JAK inhibitor-refractory MF. |
| Durability of Response |
| Loss of response and treatment intolerance remain challenges with existing therapies. Durable clinical and biological responses would improve long-term positioning. |
| Treatment Setting |
| Broad utility across treatment lines and MF subtypes increases clinical flexibility and commercial opportunity. |
| Combination Compatibility |
| Combination therapy is becoming increasingly important as developers seek to deepen spleen, symptom, anemia and molecular responses beyond JAK inhibitor monotherapy. |
| Route and Dosing |
| MF requires chronic therapy. Convenient outpatient administration can improve adherence, persistence and competitiveness relative to infusion-based or highly monitored treatments. |
Unmet Needs & Market Dynamics
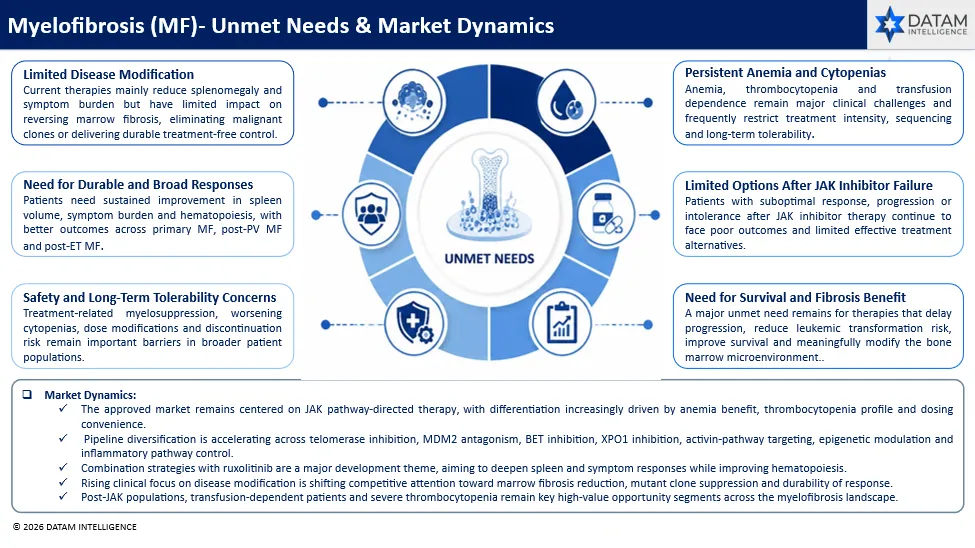
Myelofibrosis presents a significant unmet need as current therapies can reduce splenomegaly and symptom burden but do not consistently achieve durable disease modification, reversal of marrow fibrosis or sustained control of cytopenias. The treatment landscape is evolving around deeper and longer-lasting spleen and symptom responses, improvement in anemia and transfusion dependence, activity in thrombocytopenic and post-JAK inhibitor populations, reduced treatment-related myelosuppression and development of therapies capable of suppressing malignant clones, modifying the bone marrow microenvironment and delaying disease progression or leukemic transformation.
Strategic Summary
Myelofibrosis remains a rare but clinically complex hematologic malignancy characterized by substantial heterogeneity in disease biology, symptom burden, cytopenias and progression risk. The current treatment landscape is dominated by JAK pathway-directed therapies, but important gaps remain in patients with anemia, severe thrombocytopenia, suboptimal JAK inhibitor response and progressive disease.
Competitive differentiation is increasingly shifting beyond spleen-volume reduction and symptom control toward improved hematopoiesis, durable anemia benefit, reduced transfusion dependence and preservation of platelet counts. Emerging therapies are also being evaluated for their ability to modify underlying disease biology through suppression of malignant clones, reduction of marrow fibrosis and modulation of inflammatory or epigenetic pathways.
The pipeline is becoming increasingly mechanism-diverse, with late-stage programs targeting XPO1, MDM2, telomerase, BET proteins, activin signaling and other non-JAK pathways, frequently in combination with established JAK inhibitors. This reflects a broader transition toward combination and phenotype-directed treatment strategies.
Future market leadership will depend on demonstrating durable efficacy across clinically difficult MF populations, favorable long-term safety and meaningful disease modification. Therapies capable of simultaneously controlling splenomegaly and symptoms while improving cytopenias and delaying progression are likely to achieve the strongest clinical and commercial differentiation.
Why Buy Our Myelofibrosis (MF) Competitive Intelligence Report?
The myelofibrosis market is entering a more clinically differentiated and mechanism-driven phase, with established JAK inhibitors increasingly challenged by combination strategies and emerging therapies targeting XPO1, telomerase, MDM2, BET proteins, activin signaling and other disease-relevant pathways. As treatment options expand, companies require clear intelligence on spleen and symptom responses, anemia benefit, transfusion dependence, platelet eligibility, post-JAK activity, safety, durability and potential disease modification. Our report translates this evolving therapeutic landscape into actionable clinical, portfolio and commercial strategies.
Identify where competition is intensifying
Understand how approved therapies including Jakafi, Jakafi XR, Inrebic, Vonjo and Ojjaara are shaping treatment selection while tracking late-stage and emerging assets targeting XPO1, telomerase, MDM2, BET and other non-JAK pathways.
Prioritize the right patient segments
Assess commercially relevant populations across primary MF, post-PV MF and post-ET MF, including patients with anemia, severe thrombocytopenia, transfusion dependence, inadequate JAK inhibitor response and treatment intolerance.
Evaluate asset differentiation
Compare therapies across SVR35, TSS50, anemia response, transfusion independence, platelet eligibility, durability, safety, marrow fibrosis, molecular response and survival-related outcomes.
Anticipate treatment sequencing
Evaluate where emerging monotherapies and JAK inhibitor combinations could fit across frontline, suboptimal-response and post-JAK settings, and identify potential displacement or combination opportunities.
Identify future competitive white space
Determine where unmet need remains highest across cytopenia management, disease modification, malignant-clone suppression, fibrosis improvement, leukemic progression and durable hematologic recovery.
