


Diabetic retinopathy is transitioning into a more strategically segmented treatment market as established anti-VEGF standards face increasing pressure from biosimilars, higher-dose formulations and next-generation durable delivery platforms. The approved landscape remains anchored by LUCENTIS, EYLEA and EYLEA HD, but competitive intensity is rising as ranibizumab and aflibercept biosimilars expand access and compress differentiation based solely on efficacy. Epidemiological evidence in the report reinforces a sizeable addressable population, while commercial opportunity is increasingly concentrated in patients with high-risk NPDR where preventing progression before irreversible retinal damage offers the greatest potential value. Competitive positioning is therefore shifting toward durability, earlier intervention, reduced injection frequency, treatment convenience and preservation of long-term visual function.
The pipeline reflects a broader strategic move beyond conventional VEGF blockade toward sustained VEGF/VEGFR inhibition, gene therapy, Sema3A modulation, AOC3/VAP-1 inhibition, endothelin-pathway targeting and Ref-1 inhibition. Programs such as Zenkuda, AXPAXLI, sura-vec, BI 764524, oruvestat and PER-001 represent distinct approaches to improving durability, retinal perfusion and treatment burden. Future market leadership will depend less on incremental anatomical response and more on demonstrating credible prevention of NPDR-to-PDR progression, durable DRSS improvement, strong ocular safety, reduced clinic dependency and evidence of disease modification. Assets combining differentiated biology with scalable administration and clear real-world treatment advantages are likely to command the strongest clinical and commercial positioning.
Key Highlights
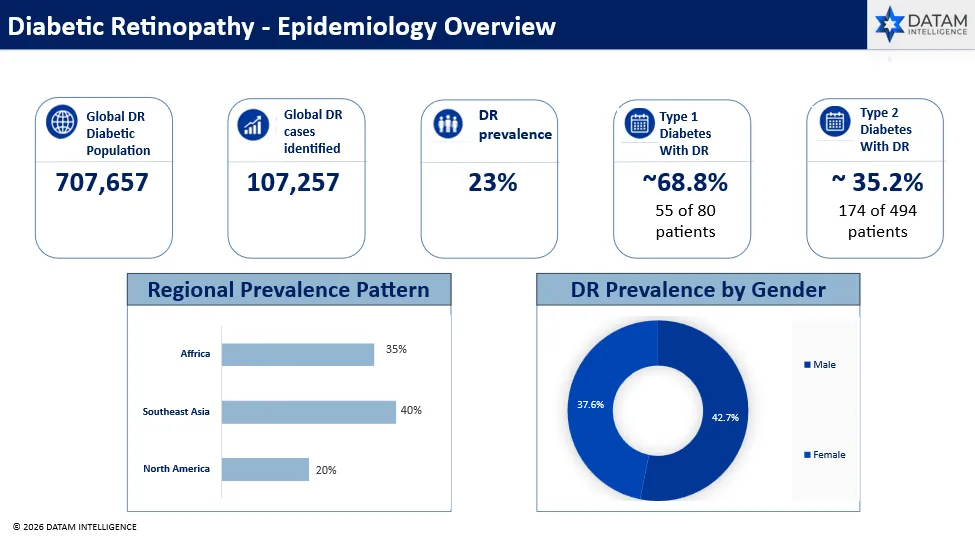
- Diabetic retinopathy represents a structurally large and progressively expanding treatment opportunity, with pooled retinal-imaging evidence covering 707,657 individuals and 107,257 DR cases, underscoring the scale of the addressable population across diabetes care.
- The approved market remains concentrated around VEGF inhibition, led by LUCENTIS, EYLEA and EYLEA HD; however, expanding ranibizumab and aflibercept biosimilars are shifting competitive pressure toward price, access, formulary positioning and treatment convenience.
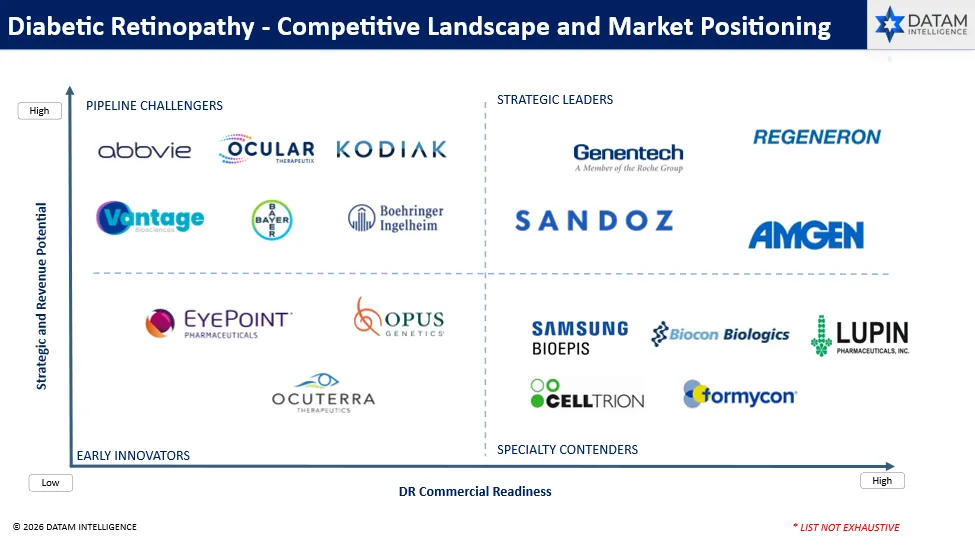
- Regeneron and Genentech/Roche retain the strongest incumbent positions through established retinal franchises, while Amgen and Sandoz are emerging as important commercial disruptors as biosimilar penetration increases across the anti-VEGF treatment class.
- Pipeline competition is moving beyond conventional short-acting VEGF blockade, with development expanding into sustained VEGF/VEGFR suppression, gene therapy, Sema3A modulation, AOC3/VAP-1 inhibition, endothelin signaling and Ref-1 targeting.
- Late-stage pipeline value is increasingly concentrated in durability and earlier intervention, with Zenkuda, AXPAXLI, sura-vec, fenofibrate and Tangning Tongluo advancing differentiated approaches aimed at reducing treatment burden and delaying progression in NPDR.
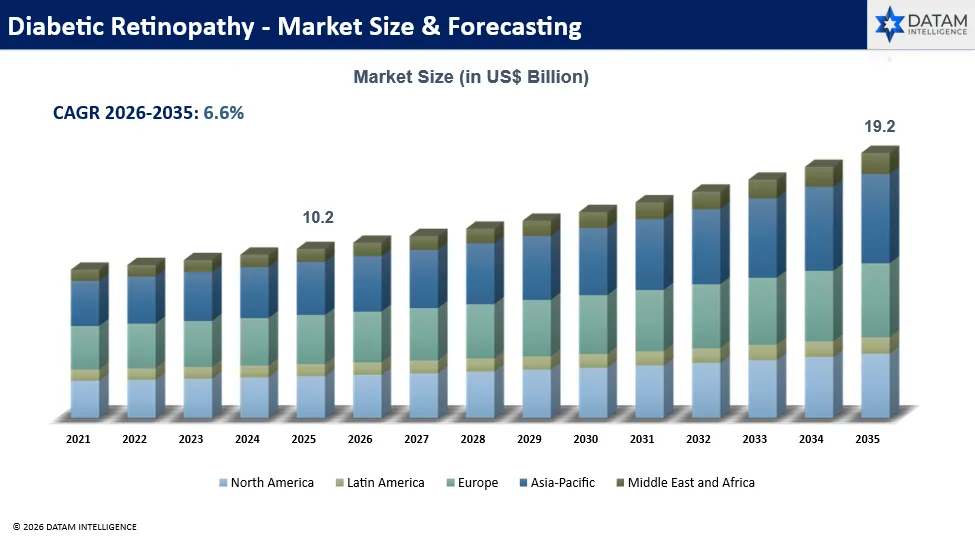
- The commercial opportunity remains attractive, with the report sizing the global diabetic retinopathy market at US$10.2 billion in 2025, rising to US$19.2 billion by 2035 at a 6.6% CAGR.
- Future leadership will be determined by clinically meaningful differentiation rather than incremental efficacy, particularly durable DRSS improvement, prevention of NPDR-to-PDR progression, lower injection frequency, strong ocular safety and credible evidence of disease modification.
Disease Overview
Diabetic retinopathy (DR) is a chronic neurovascular complication of diabetes mellitus characterized by progressive structural and functional injury to the retinal microcirculation and neural retina. Sustained hyperglycemia induces multiple pathogenic pathways, including advanced glycation end-product formation, activation of protein kinase C, oxidative stress, polyol pathway flux, inflammation and dysregulation of vascular endothelial growth factor (VEGF). These processes promote pericyte apoptosis, endothelial dysfunction, capillary basement membrane thickening, breakdown of the blood-retinal barrier and progressive retinal capillary non-perfusion.
Clinically, DR is classified into non-proliferative diabetic retinopathy (NPDR) and proliferative diabetic retinopathy (PDR). NPDR is characterized by microaneurysms, intraretinal hemorrhages, venous abnormalities and intraretinal microvascular abnormalities, whereas progression to PDR is driven by severe retinal ischemia and hypoxia-induced angiogenic signaling, resulting in pathological neovascularization. Diabetic macular edema (DME) may develop at any stage and results from increased vascular permeability and accumulation of extracellular fluid within the macula.
Disease progression is influenced by diabetes duration, glycemic exposure, hypertension, dyslipidemia and renal dysfunction. Current management includes systemic metabolic control, intravitreal anti-VEGF agents, corticosteroids, retinal laser photocoagulation and vitreoretinal surgery. Persistent unmet needs include durable vascular stabilization, reduced treatment burden, prevention of progression from NPDR to PDR and therapies targeting upstream inflammatory and neurodegenerative mechanisms.
Epidemiology Analysis
Diabetic retinopathy (DR) represents a substantial ophthalmic complication of diabetes, with epidemiological evidence demonstrating a significant burden across both Type 1 and Type 2 diabetes populations. Recent pooled retinal-imaging evidence evaluated 707,657 individuals with diabetes and identified 107,257 DR cases, while the pooled prevalence of any DR was approximately 23% among people with diabetes. The burden varies considerably across regions, reflecting differences in diabetes prevalence, duration of disease, glycemic control, access to retinal screening and management of associated cardiovascular and metabolic risk factors.
Clinical evidence also demonstrates important variation by diabetes type. In a recent observational cohort, DR was identified in approximately 68.8% of patients with Type 1 diabetes (55 of 80 patients) compared with 35.2% of patients with Type 2 diabetes (174 of 494 patients), highlighting the strong influence of cumulative diabetes duration and metabolic exposure on retinal microvascular injury. Regional prevalence patterns further indicate heterogeneous disease burden across Africa, Southeast Asia and North America. Gender-based clinical data suggest numerically higher DR prevalence among men than women in some cohorts, although differences are not consistently statistically significant. Overall, the epidemiological profile supports continued expansion of systematic screening, earlier identification of high-risk patients and interventions aimed at preventing progression to vision-threatening disease.
Approved Drugs
The FDA-approved treatment landscape for diabetic retinopathy (DR) has evolved substantially over the past decade, progressing from a limited anti-VEGF treatment base toward a broader and increasingly differentiated ophthalmic therapeutic framework. Current approved pharmacologic therapies remain centered on VEGF pathway inhibition, targeting the abnormal vascular permeability, retinal ischemia-driven angiogenic signaling and pathological neovascularization that characterize progressive DR. Established therapies such as LUCENTIS (ranibizumab) and EYLEA (aflibercept) have been complemented by EYLEA HD (aflibercept 8 mg), which extends the durability of VEGF suppression through a higher-dose formulation. The competitive landscape has further expanded with multiple ranibizumab and aflibercept biosimilars, including CIMERLI, YESAFILI, OPUVIZ, AHZANTIVE, ENZEEVU, PAVBLU, EYDENZELT, NUFYMCO and RANLUSPEC, increasing therapeutic availability and introducing greater pricing and access competition. This expanding approved landscape is shifting differentiation beyond efficacy alone toward dosing durability, injection frequency, delivery convenience, biosimilar adoption and treatment cost. As a result, competitive positioning in diabetic retinopathy is increasingly shaped by the ability to maintain retinal vascular stability while reducing treatment burden and improving long-term patient adherence.
Brand and Generic Name | Sponsor | Current Owner | Approval Date | MOA |
LUCENTIS (Ranibizumab) | Genentech, Inc. | Genentech, Inc. / Roche Group | April, 2017 | Humanized anti-VEGF-A Fab fragment that binds biologically active VEGF-A isoforms and prevents VEGFR-1/VEGFR-2 activation, thereby reducing retinal vascular permeability, endothelial proliferation and pathological neovascularization. |
EYLEA (Aflibercept) | Regeneron Pharmaceuticals, Inc. | Regeneron Pharmaceuticals, Inc. | May, 2019 | Recombinant VEGF-receptor fusion protein that functions as a high-affinity soluble decoy receptor for VEGF-A and placental growth factor, preventing ligand activation of endogenous VEGF receptors and suppressing retinal angiogenesis and vascular leakage. |
CIMERLI (Ranibizumab-eqrn) | Coherus BioSciences, Inc. | Sandoz Inc. | August, 2022 | Ranibizumab biosimilar that neutralizes VEGF-A before receptor engagement, reducing VEGF-driven endothelial-cell proliferation, vascular permeability and abnormal retinal neovascularization. |
EYLEA HD (Aflibercept 8 mg) | Regeneron Pharmaceuticals, Inc. | Regeneron Pharmaceuticals, Inc. | August, 2023 | High-dose aflibercept formulation providing greater intraocular molar exposure while retaining the VEGF-trap mechanism of aflibercept through sequestration of VEGF-A and placental growth factor and inhibition of downstream VEGFR signaling. |
YESAFILI (Aflibercept-jbvf) | Biocon Biologics Ltd. | Biocon Biologics Ltd. | May, 2024 | Aflibercept biosimilar acting as a soluble VEGF receptor decoy that captures VEGF-A and placental growth factor, limiting receptor-mediated angiogenic signaling and retinal vascular hyperpermeability. |
OPUVIZ (Aflibercept-yszy) | Samsung Bioepis Co., Ltd. | Samsung Bioepis Co., Ltd. | May, 2024 | Aflibercept biosimilar that competitively sequesters VEGF-A and placental growth factor, preventing their interaction with cell-surface VEGF receptors and thereby suppressing pathological retinal angiogenesis. |
AHZANTIVE (Aflibercept-mrbb) | Formycon AG | Klinge Biopharma GmbH | June, 2024 | Aflibercept biosimilar with high-affinity ligand-trapping activity against VEGF-A and placental growth factor, reducing VEGFR-mediated endothelial activation, neovascularization and vascular leakage. |
ENZEEVU (Aflibercept-abzv) | Sandoz Inc. | Sandoz Group AG | August, 2024 | VEGF-trap biosimilar that binds circulating VEGF-A and placental growth factor before receptor activation, attenuating pro-angiogenic signaling and abnormal retinal vascular permeability. |
PAVBLU (Aflibercept-ayyh) | Amgen Inc. | Amgen Inc. | August, 2024 | Aflibercept biosimilar that forms inactive complexes with VEGF-A and placental growth factor, thereby inhibiting VEGFR signaling responsible for pathological angiogenesis and increased vascular permeability. |
EYDENZELT (Aflibercept-boav) | Celltrion, Inc. | Celltrion, Inc. | October, 2025 | Aflibercept biosimilar that acts extracellularly as a ligand sink for VEGF-A and placental growth factor, reducing angiogenic stimulation and stabilization failure within the retinal microvasculature. |
NUFYMCO (Ranibizumab-leyk) | Formycon AG / Bioeq AG | Formycon / Bioeq; Zydus Lifesciences is U.S. commercialization partner | December, 2025 | Ranibizumab biosimilar comprising an anti-VEGF-A monoclonal antibody fragment that blocks VEGF-A interaction with VEGFR-1 and VEGFR-2, thereby reducing endothelial proliferation and retinal vascular leakage. |
RANLUSPEC (Ranibizumab-hkdz) | Lupin Limited | Lupin Limited | June, 2026 | Ranibizumab biosimilar that selectively binds VEGF-A and inhibits downstream VEGF-receptor signaling associated with pathological neovascularization and increased permeability of retinal vessels. |
LUCENTIS (Ranibizumab)-Recent Updates
FDA currently lists the LUCENTIS (ranibizumab) 0.5 mg/0.05 mL and 0.3 mg/0.05 mL single-dose vial presentations as discontinued, while both corresponding pre-filled syringe presentations remain actively marketed.
Available U.S. prescribing information indicates that the transition had occurred by August 2023, when the LUCENTIS label was revised to list only the 0.5 mg and 0.3 mg pre-filled syringe presentations. FDA does not provide a separate exact commercial discontinuation date for the vial presentations.
The discontinuation is presentation-specific rather than a regulatory withdrawal of LUCENTIS. The biologics license and diabetic retinopathy indication remain active, meaning ranibizumab continues to participate in the U.S. DR treatment landscape.
Strategically, the change reflects delivery-format consolidation toward pre-filled syringes, which reduce preparation steps compared with vial-based administration, rather than an efficacy- or safety-driven exit of the molecule.
| Drug Name | Company Name | Route | Discontinued Presentation | Date of Discontinuation / Withdrawal | Current Regulatory Status |
LUCENTIS (Ranibizumab) | Genentech, Inc. / Roche | Intravitreal | 0.5 mg/0.05 mL Single-Dose Vial | By August 2023 | Partially Discontinued -Pre-filled syringe remains active |
LUCENTIS (Ranibizumab) | 0.3 mg/0.05 mL Single-Dose Vial |
Pipeline Analysis
As of August 2026, the diabetic retinopathy therapeutic pipeline is increasingly focused on mechanisms beyond conventional short-acting VEGF inhibition. Investigational strategies target sustained VEGF/VEGFR suppression, retinal ischemia, endothelial dysfunction, inflammatory signaling, AOC3/VAP-1 activity, Sema3A-mediated vascular injury, integrin pathways and metabolic microvascular dysfunction. Long-acting intravitreal implants, oral small molecules and gene therapies are being developed to reduce injection burden, extend treatment durability and intervene earlier in non-proliferative disease. Overall, the pipeline is shifting toward mechanism-driven and potentially disease-modifying approaches aimed at stabilizing retinal vasculature, improving perfusion, limiting progression from NPDR to PDR and preserving long-term visual function:
| Sponsor | Intervention | Clinical Stage | MoA | RoA | Modality | |||
| Kodiak Sciences | Zenkuda (Tarcocimab Tedromer / KSI-301) | Phase 3 - Completed | VEGF-A inhibition using an antibody-biopolymer conjugate designed for prolonged VEGF suppression | Intravitreal | Antibody-Biopolymer Conjugate | |||
| Ocular Therapeutix | AXPAXLI (OTX-TKI / Axitinib Implant) | Phase 3 | Sustained VEGFR-1, VEGFR-2 and VEGFR-3 tyrosine kinase inhibition, suppressing VEGF-mediated retinal vascular pathology | Intravitreal | Small Molecule Sustained-Release Implant | |||
| AbbVie / REGENXBIO | Surabgene Lomparvovec (Sura-vec / ABBV-RGX-314) | Phase 2/3 | AAV8-mediated delivery of a gene encoding an anti-VEGF Fab for sustained intraocular VEGF inhibition | Suprachoroidal | AAV Gene Therapy | |||
Beletalent (Zhuhai) Pharmaceutical | Tangning Tongluo Tablets (TNTL) | Phase 3 | Multicomponent modulation of retinal microvascular dysfunction and inflammatory pathways | Oral | Multicomponent Botanical Therapy | |||
Jaeb Center for Health Research / DRCR Retina Network | Fenofibrate | Phase 3 | PPAR-伪 activation modulates lipid metabolism, inflammation and endothelial signaling associated with retinal microvascular injury | Oral | Small Molecule | |||
| Boehringer Ingelheim | BI 764524 | Phase 2 | Sema3A inhibition designed to reduce ischemia-associated retinal vascular dysfunction and support physiological revascularization | Intravitreal | Monoclonal Antibody | |||
| Vantage Biosciences | Oruvestat (VX-01) | Phase 2 | Selective AOC3/VAP-1 inhibition reduces leukocyte trafficking and vascular inflammatory signaling | Oral | Small Molecule | |||
Bayer / Perfuse Therapeutics | PER-001 | Phase 2 - Completed | Endothelin receptor antagonism designed to improve retinal perfusion and reduce ischemia-associated retinal injury | Intravitreal | Small Molecule Sustained-Release Implant | |||
Opus Genetics / Ocuphire Pharma | APX3330 | Phase 2 - Completed; Phase 3-Ready | APE1/Ref-1 redox inhibition suppresses inflammatory and angiogenic transcriptional signaling including HIF-1伪, NF-魏B and AP-1 | Oral | Small Molecule | |||
| Bayer | Runcaciguat (BAY 1101042) | Phase 2 - Completed | Soluble guanylate cyclase activation increases cGMP signaling and supports retinal microvascular function | Oral | Small Molecule | |||
| EyePoint Pharmaceuticals | DURAVYU (EYP-1901 / Vorolanib) | Phase 2 - Completed | Sustained pan-VEGFR tyrosine kinase inhibition suppresses VEGF-driven angiogenesis and vascular leakage | Intravitreal | Small Molecule Sustained-Release Insert | |||
| OcuTerra Therapeutics | Nesvategrast (OTT166) | Phase 2 -Completed | Inhibition of RGD-binding integrins involved in angiogenesis, vascular permeability, inflammation and fibrosis | Ophthalmic | Small Molecule | |||
| Boehringer Ingelheim | BI 765128 | Phase 1/2 | NRP1 inhibition designed to modulate pathological retinal vascular signaling | Intravitreal | Monoclonal Antibody | |||
| Hoffmann-La Roche | RO7663498 | Phase 1 | Molecular target and detailed mechanism have not yet been publicly disclosed sufficiently for confident assignment | Intravitreal | Investigational Biologic | |||
Market Size & Forecasting
The global diabetic retinopathy market stood at US$10.2 billion in 2025 and is expected to reach US$19.2 billion by 2035, growing with a CAGR of 6.6% during the forecast period 2026-2035.
Competitive Landscape and Market Positioning
The diabetic retinopathy competitive landscape is increasingly differentiated by regulatory maturity, retinal commercial infrastructure, treatment durability, delivery innovation and the ability to intervene earlier in non-proliferative disease. Regeneron, Genentech/Roche, Amgen and Sandoz occupy the Strategic Leaders quadrant based on FDA-approved diabetic retinopathy products, established ophthalmology franchises and high commercial readiness. Regeneron is particularly well positioned through the EYLEA and EYLEA HD franchise, while Genentech/Roche retains a long-standing anti-VEGF presence through LUCENTIS. Amgen and Sandoz strengthen the competitive intensity through approved aflibercept and ranibizumab biosimilars.
The Pipeline Challengers quadrant includes Kodiak Sciences, Ocular Therapeutix, AbbVie/REGENXBIO, Boehringer Ingelheim, Bayer and Vantage Biosciences, reflecting differentiated late-stage or mid-stage programs focused on prolonged VEGF suppression, sustained-release delivery, gene therapy, retinal ischemia and inflammatory vascular pathways. Opus Genetics, EyePoint Pharmaceuticals and OcuTerra Therapeutics remain Early Innovators with differentiated but less commercially mature DR programs. Biocon Biologics, Samsung Bioepis, Formycon/Klinge Biopharma, Celltrion and Lupin are positioned as Specialty Contenders, supported primarily by biosimilar portfolios and expanding market access. Overall, competition is shifting beyond conventional anti-VEGF efficacy toward longer treatment durability, reduced injection burden, earlier NPDR intervention, non-VEGF biology and potentially disease-modifying approaches.
Target Opportunity Profile (TOP)
To compete effectively against established diabetic retinopathy therapies such as LUCENTIS, EYLEA, EYLEA HD and emerging aflibercept and ranibizumab biosimilars, next-generation therapies must demonstrate a superior Target Opportunity Profile across several critical dimensions. Competitive differentiation will increasingly depend on achieving durable DRSS improvement, sustained prevention of progression from NPDR to PDR, reduced development of vision-threatening complications and preservation of visual function, while materially lowering the burden of repeated intravitreal injections. Greater value will come from therapies that offer 6-12 month durability, oral or less invasive administration, strong ocular and systemic safety and efficacy in patients with high-risk NPDR before irreversible retinal damage occurs. The highest-value emerging therapies will also need to demonstrate evidence of disease modification, including improved retinal perfusion, vascular stabilization, attenuation of ischemic and inflammatory pathways and durable suppression of disease progression beyond VEGF inhibition alone. Therapies that combine clinically meaningful efficacy with lower treatment frequency, broader patient eligibility, convenient administration and reduced long-term management burden will be best positioned to challenge entrenched anti-VEGF standards of care.
Target Opportunity Profile (TOP) - Competitive Attributes
| Dimension | Desired Profile for Emerging Therapies | Rationale |
| Safety |
| DR patients often require prolonged therapy and may have substantial cardiovascular, renal and metabolic comorbidities. New therapies must therefore demonstrate strong ocular tolerability without adding clinically meaningful systemic risk. |
| Efficacy |
| Existing anti-VEGF therapies can improve DR severity, but differentiation increasingly depends on preventing progression and maintaining retinal vascular stability before irreversible structural damage develops. |
| Durability |
| Frequent intravitreal dosing remains a major practical limitation. Extended durability can improve adherence, reduce clinic burden and strengthen real-world effectiveness. |
| Route of Administration |
| Non-invasive and long-acting administration could materially differentiate emerging therapies from conventional anti-VEGF injections and broaden treatment feasibility in earlier-stage NPDR. |
| Mechanistic Differentiation |
| VEGF inhibition controls downstream vascular pathology but does not fully address upstream ischemic, inflammatory and neurodegenerative drivers. Therapies acting on complementary biology may improve long-term disease control. |
| Early-Stage Intervention |
| A major opportunity lies in shifting treatment from reactive management of advanced disease toward earlier prevention of irreversible retinal damage. |
| Treatment Burden |
| DR affects a large chronic population. Lower treatment burden can improve persistence and reduce operational pressure on retinal practices. |
| Visual Function Preservation |
| Prevention of irreversible visual decline remains the principal clinical objective, particularly as DR progresses toward proliferative disease. |
| Real-World Applicability |
| Highly selective trial populations may limit commercial relevance. Broad applicability is important because real-world DR patients frequently have multimorbidity and inconsistent follow-up. |
| Commercial Differentiation |
| Future entrants must compete against established aflibercept and ranibizumab franchises plus lower-cost biosimilars. Incremental efficacy alone may be insufficient without meaningful convenience or economic differentiation. |
Unmet Needs & Market Dynamics
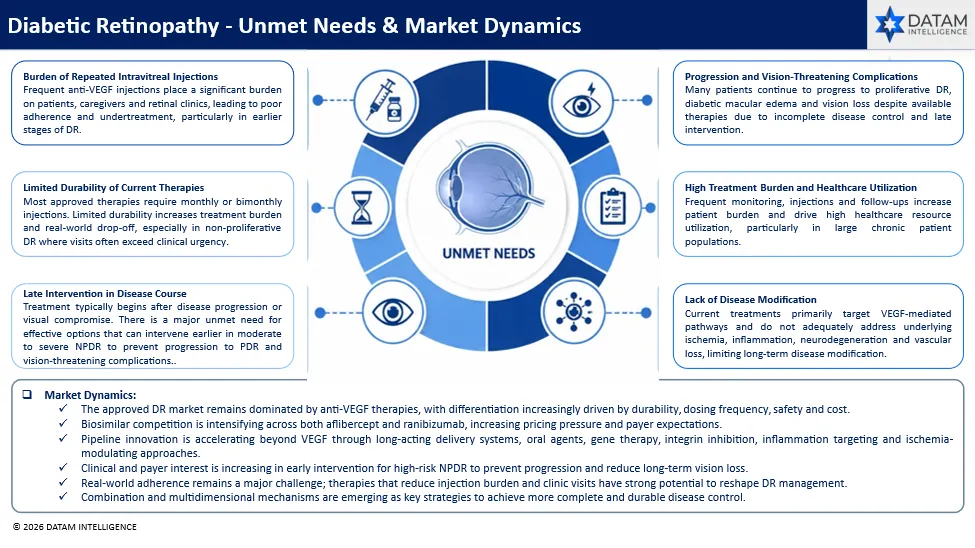
Diabetic retinopathy presents a significant unmet need as current therapies can reduce VEGF-driven vascular leakage and slow progression, but do not consistently deliver durable disease control, reverse retinal ischemia or eliminate the need for repeated intravitreal treatment. The treatment landscape is evolving around longer-lasting suppression of disease activity, earlier intervention in high-risk NPDR, prevention of progression to PDR and vision-threatening complications, reduced injection and monitoring burden, improved treatment adherence and broader activity beyond conventional VEGF inhibition. Increasing emphasis is also being placed on therapies capable of addressing underlying inflammatory signaling, endothelial dysfunction, neurovascular injury and impaired retinal perfusion, while preserving visual function over the long term. Emerging approaches such as sustained-release implants, oral agents and gene therapies are therefore being positioned to provide more durable vascular stabilization, reduce dependence on frequent injections and potentially achieve deeper modification of the underlying retinal disease process.
Strategic Summary
Diabetic retinopathy remains a progressive and clinically heterogeneous microvascular complication of diabetes, with disease burden shaped by retinal ischemia, vascular leakage, neurovascular dysfunction and risk of progression from NPDR to PDR and vision-threatening complications. The current treatment landscape is dominated by VEGF pathway-directed therapies, but important gaps remain in treatment durability, early-stage intervention, adherence and prevention of irreversible retinal damage.
Competitive differentiation is increasingly shifting beyond short-term anatomical improvement toward sustained DRSS improvement, prevention of NPDR-to-PDR progression, preservation of visual function and reduction in injection frequency. Greater value is also being placed on therapies that can address underlying disease biology, including retinal ischemia, inflammation, endothelial dysfunction and neurovascular injury rather than relying exclusively on downstream VEGF suppression.
The pipeline is becoming increasingly mechanism-diverse, with emerging programs spanning long-acting VEGF/VEGFR inhibition, sustained-release implants, oral AOC3/VAP-1 and Ref-1 pathway inhibition, Sema3A-targeted approaches and gene therapy-mediated anti-VEGF expression. This reflects a broader transition toward durable, less invasive and potentially disease-modifying strategies, particularly in high-risk NPDR populations where earlier intervention may prevent progression to advanced disease.
Future market leadership will depend on demonstrating durable efficacy, reduced treatment burden, strong ocular and systemic safety and meaningful prevention of vision-threatening progression. Therapies capable of combining prolonged disease control with convenient administration and activity beyond conventional VEGF inhibition are likely to achieve the strongest clinical and commercial differentiation.
Why Buy Our Diabetic Retinopathy Competitive Intelligence Report?
The diabetic retinopathy market is entering a more differentiated and innovation-driven phase, with established anti-VEGF therapies increasingly challenged by longer-acting formulations, biosimilars, sustained-release delivery systems, oral therapies and gene therapy approaches. As competition expands beyond conventional VEGF suppression, companies require clear intelligence on DRSS improvement, prevention of NPDR-to-PDR progression, durability, injection burden, visual outcomes, retinal perfusion, safety and potential disease modification. Our report translates this evolving therapeutic landscape into actionable clinical, portfolio and commercial strategies.
Identify where competition is intensifying
Understand how approved therapies including LUCENTIS, EYLEA, EYLEA HD and expanding ranibizumab and aflibercept biosimilars are reshaping treatment selection while tracking emerging assets across sustained VEGF inhibition, gene therapy, vascular regeneration, inflammatory signaling and ischemia-modulating mechanisms.
Prioritize the right patient segments
Assess commercially relevant populations across moderate-to-severe NPDR, high-risk NPDR, PDR and patients at elevated risk of vision-threatening progression, including populations with preserved vision who may benefit from earlier intervention.
Evaluate asset differentiation
Compare therapies across DRSS response, progression to PDR or DME, BCVA preservation, dosing durability, injection frequency, route of administration, retreatment requirements, ocular safety and systemic tolerability to identify clinically meaningful competitive advantages.
Assess durability and treatment burden
Benchmark emerging therapies against current anti-VEGF standards on 6–12 month treatment durability, reduction in injection frequency, clinic-visit requirements and real-world adherence, increasingly important determinants of physician and patient adoption.
Track innovation beyond VEGF
Evaluate how AOC3/VAP-1 inhibition, Sema3A targeting, Ref-1 modulation, endothelin-pathway intervention, integrin inhibition, sustained-release TKIs and AAV-based gene therapies could reshape the future DR treatment paradigm.
Anticipate future market leadership
Identify which assets are best positioned to move DR management from reactive treatment of advanced disease toward earlier, durable and potentially disease-modifying intervention, helping inform licensing, partnering, clinical-development prioritization and commercial strategy.
