


Primary Biliary Cholangitis (PBC) is entering a more segmented and competitive treatment era as management expands beyond first-line ursodiol. IQIRVO and LIVDELZI have established differentiated PPAR-targeted options for adults with an inadequate response or intolerance to ursodiol, while LYNAVOY has created a dedicated treatment segment for PBC-associated cholestatic pruritus. FDA’s withdrawal of OCALIVA in November 2025 further consolidated branded second-line competition around the newer PPAR therapies.
Early commercial performance indicates an emerging leadership advantage for LIVDELZI. The product generated US$371 million in 2025 compared with US$210 million for IQIRVO and maintained its lead during the first half of 2026. Future market share, however, will increasingly depend on biochemical response, hepatic safety, symptom improvement, treatment convenience, specialist confidence, payer access and confirmation of long-term clinical benefit.
Pipeline competition is broadening across PPAR modulation, FXR agonism, IBAT inhibition, NOX inhibition, immune-tolerance restoration and symptom-directed mechanisms. Saroglitazar represents the most advanced near-term challenger, while CS0159, pemafibrate, volixibat and setanaxib could further reshape treatment sequencing. Sustainable differentiation will require evidence extending beyond alkaline phosphatase reduction to bilirubin control, fibrosis stabilization, durable pruritus relief and delayed progression to cirrhosis, hepatic decompensation, transplantation or liver-related mortality.
Key Highlights
- The PBC treatment landscape has progressed beyond ursodiol-led management toward a segmented model encompassing biochemical control, symptom management and long-term disease modification.
- IQIRVO and LIVDELZI have established differentiated PPAR-targeted second-line options for adults with an inadequate response or intolerance to ursodiol, strengthening competition around efficacy, safety and access.
- LYNAVOY’s March 2026 approval created a dedicated treatment segment for PBC-associated cholestatic pruritus, complementing disease-directed therapies and expanding combination-treatment opportunities.
- LIVDELZI established early commercial leadership, generating US$371 million in 2025 compared with US$210 million for IQIRVO and maintaining its lead during the first half of 2026.
- Saroglitazar represents the most advanced near-term challenger, while CS0159, pemafibrate, volixibat and setanaxib broaden pipeline competition across PPAR, FXR, IBAT and NOX-related mechanisms.
- Persistent unmet need remains concentrated among inadequate ursodiol responders and patients experiencing progressive fibrosis, pruritus, fatigue or cognitive impairment despite biochemical improvement.
- Future market leadership will require durable biochemical normalization, symptom relief, favorable hepatic safety, fibrosis control and credible evidence of delayed progression to cirrhosis, hepatic decompensation or transplantation.
Disease Overview
Primary biliary cholangitis (PBC) is a chronic, immune-mediated cholestatic liver disease characterized by progressive destruction of small intrahepatic bile ducts. Continued duct injury impairs bile flow, promotes portal inflammation and drives fibrosis that may advance to cirrhosis, portal hypertension and liver failure. PBC predominantly affects women, while men may be diagnosed at an older age and present with more advanced disease features. Many patients are asymptomatic at diagnosis, although fatigue and pruritus create clinical burden. Diagnosis relies on cholestatic liver tests and antimitochondrial antibodies. Early identification, risk stratification and sustained biochemical response are central to delaying progression and improving outcomes.
Epidemiology Analysis
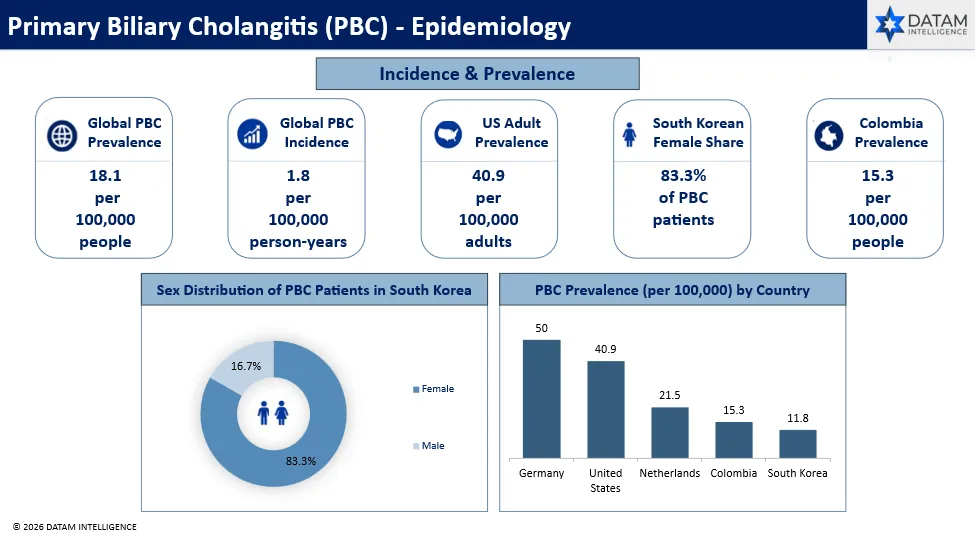
PBC epidemiology demonstrates marked geographic, sex and age variation, with prevalence consistently concentrated among women and older adults. Recent global evidence estimates prevalence at 18.1 cases per 100,000 people and incidence at 1.8 cases per 100,000 person-years. Country estimates range from 11.8 per 100,000 in South Korea to 50 per 100,000 in Germany, reflecting differences in diagnostic intensity, healthcare access and data methodology. South Korean evidence indicates that women represent 83.3% of diagnosed patients. Rising recognition and improved survival are expanding the prevalent population, strengthening demand for earlier diagnosis, specialist referral, biochemical monitoring and optimized treatment sequencing across care pathways.
Approved Drugs
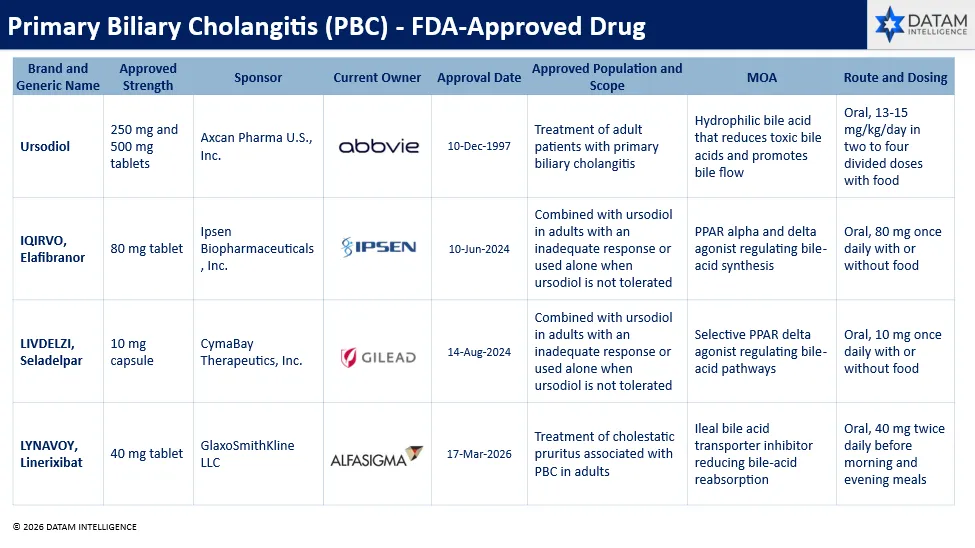
- The FDA-approved PBC treatment landscape now combines foundational disease management, mechanism-driven second-line intervention and dedicated control of cholestatic pruritus, creating a more differentiated therapeutic and commercial environment.
- Ursodiol remains the established first-line therapy, improving bile composition and flow; however, incomplete biochemical response sustains considerable demand for effective second-line treatment options.
- IQIRVO and LIVDELZI, approved within two months of each other in 2024, transformed second-line competition through differentiated PPAR activation and comparable positioning among ursodiol-inadequate responders.
- IQIRVO activates PPAR alpha and delta pathways, while LIVDELZI selectively targets PPAR delta, making biochemical response, tolerability, prescriber confidence and payer access central competitive differentiators.
- Both therapies received accelerated approval based on alkaline phosphatase reduction. Confirmatory outcomes, long-term safety and evidence of reduced disease progression will determine regulatory durability and treatment sequencing.
- LYNAVOY’s March 2026 approval expanded the commercial landscape into PBC-associated cholestatic pruritus. Its ileal bile acid transporter inhibition supports complementary use rather than direct substitution for disease-directed therapies. The portfolio now combines a generic first-line foundation, two competing branded second-line treatments and a dedicated symptom-control product, creating distinct opportunities across patient identification, specialist engagement, formulary positioning, combination use and evidence generation.
Post-Launch Revenue Analysis
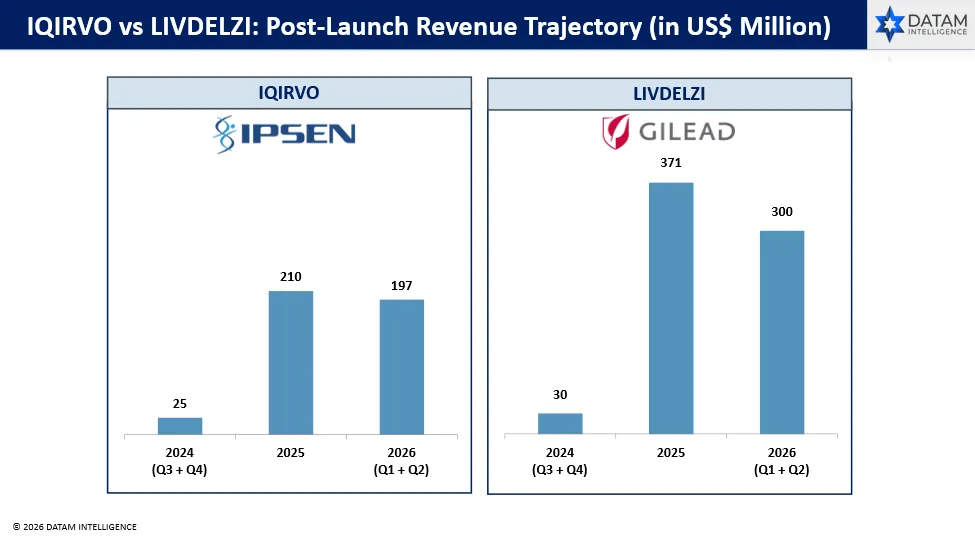
- LIVDELZI Establishes Early Commercial Leadership: LIVDELZI generated US$371 million in 2025, approximately 77% above IQIRVO’s US$210 million, demonstrating stronger first-full-year market penetration despite its later FDA approval.
- Revenue Advantage Continues Into 2026: During the first half of 2026, LIVDELZI recorded US$300 million compared with IQIRVO’s US$197 million, maintaining a 52% revenue lead and indicating faster prescriber conversion.
- Competitive Differentiation Is Becoming Critical: Sustaining growth will increasingly depend on biochemical response, pruritus benefits, safety, payer access, specialist engagement and confirmatory outcomes rather than launch timing alone. First-half 2026 figures should not be directly compared with full-year 2025 revenue.
Discontinuation and Regulatory Withdrawal Analysis
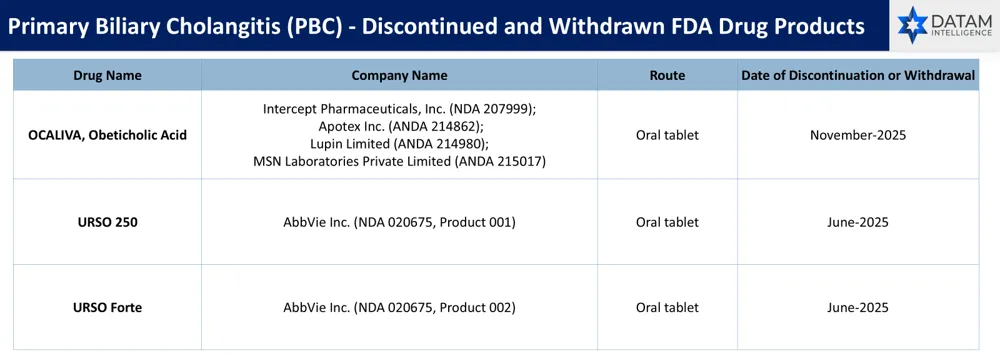
- FDA withdrew OCALIVA and three associated generic applications on November 24, 2025, removing obeticholic acid from the US PBC treatment landscape.
- The required postmarketing trial failed to verify clinical benefit, while FDA identified excess liver transplants and deaths among OCALIVA-treated patients with early-stage PBC.
- AbbVie discontinued the branded URSO 250 and URSO Forte products in June 2025, marking the exit of both legacy ursodiol brands from the US market.
- These exits have restructured the competitive landscape around generic ursodiol as the first-line treatment and IQIRVO and LIVDELZI as the principal branded second-line therapies.
FDA New Drug Application Approval Timeline
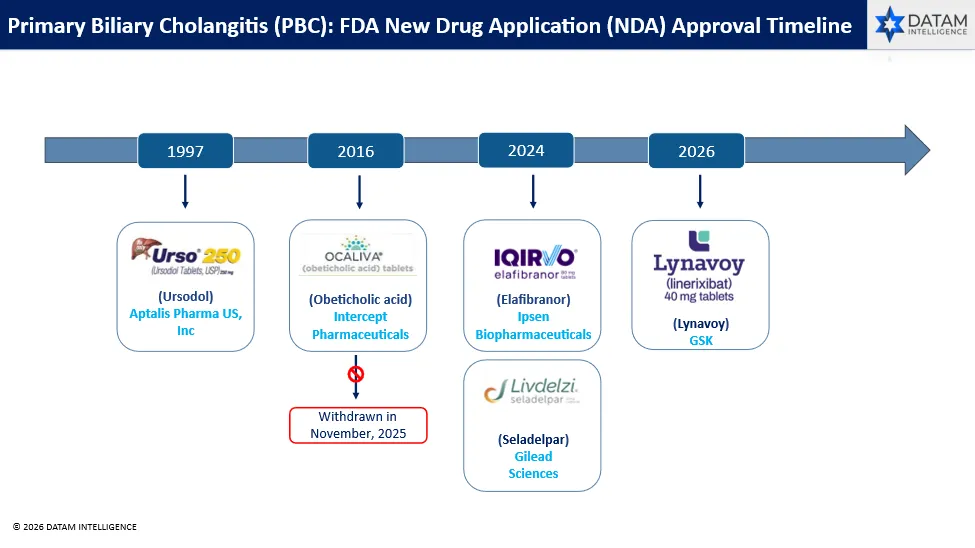
The FDA approval timeline illustrates the evolution of PBC treatment from foundational bile-acid therapy toward mechanism-based and symptom-directed medicines. URSO 250, approved under NDA 020675 in 1997, established ursodiol as first-line treatment. OCALIVA, NDA 207999, introduced FXR agonism in 2016 but was withdrawn in November 2025. IQIRVO, NDA 218860, and LIVDELZI, NDA 217899, received approval in 2024, expanding second-line treatment through differentiated PPAR activation. LYNAVOY, NDA 220295, was approved in March 2026 for PBC-associated cholestatic pruritus. The progression demonstrates increasing treatment segmentation across biochemical control, inadequate ursodiol response and persistent symptom management.
Pipeline Analysis
As of July 2026, the therapeutic pipeline for primary biliary cholangitis (PBC) is robust, encompassing various modalities aimed at slowing disease progression and preserving vision. Here's an overview of key investigational therapies across different classes:
| fn | Asset | Current Stage | Mechanism | Route | Modality |
| Zydus Therapeutics | Saroglitazar Magnesium | Registration | Dual PPAR alpha and gamma agonist | Oral | Small molecule |
| Cascade Pharmaceuticals | CS0159 | Phase III | Nonsteroidal FXR agonist | Oral | Small molecule |
| Kowa Research Institute | K-808, Pemafibrate | Phase II | Selective PPAR-alpha modulator | Oral | Small molecule |
Calliditas Therapeutics, part of Asahi Kasei | Setanaxib | Phase IIb | NOX1 and NOX4 inhibitor | Oral | Small molecule |
| Mirum Pharmaceuticals | Volixibat | Phase IIb | IBAT inhibitor | Oral | Small molecule |
| COUR Pharmaceuticals | CNP-104 | Phase IIa | PDC-E2 tolerizing nanoparticle | Intravenous | Nanoparticle immunotherapy |
| Umecrine Cognition | Golexanolone | Phase Ib/IIa | GABA-A steroid antagonist | Oral | Small molecule |
| Parvus Therapeutics | PVT201 | Phase I completed | Treg-inducing pMHC nanomedicine | Intravenous | Nanomedicine |
* LIST NOT EXHAUSTIVE
Market Size & Forecasting
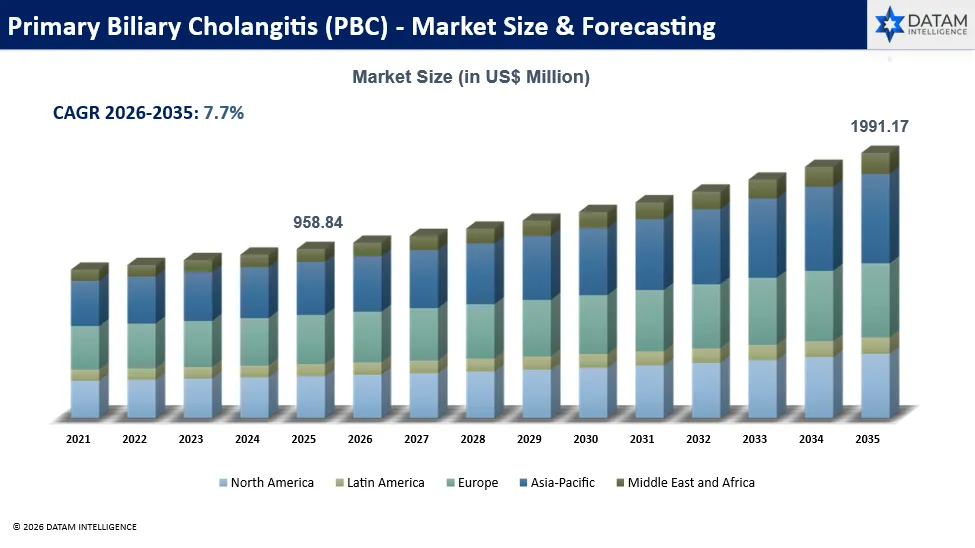
The global primary biliary cholangitis (PBC) treatment market stood at US$ 958.84 million in 2025 and is expected to reach US$ 1991.17 million by 2035, growing with a CAGR of 7.7% during the forecast period 2026-2035.
Competitive Landscape and Market Positioning
- The PBC market is transitioning from ursodiol-led management toward differentiated therapies targeting biochemical control, symptom burden and long-term disease progression.
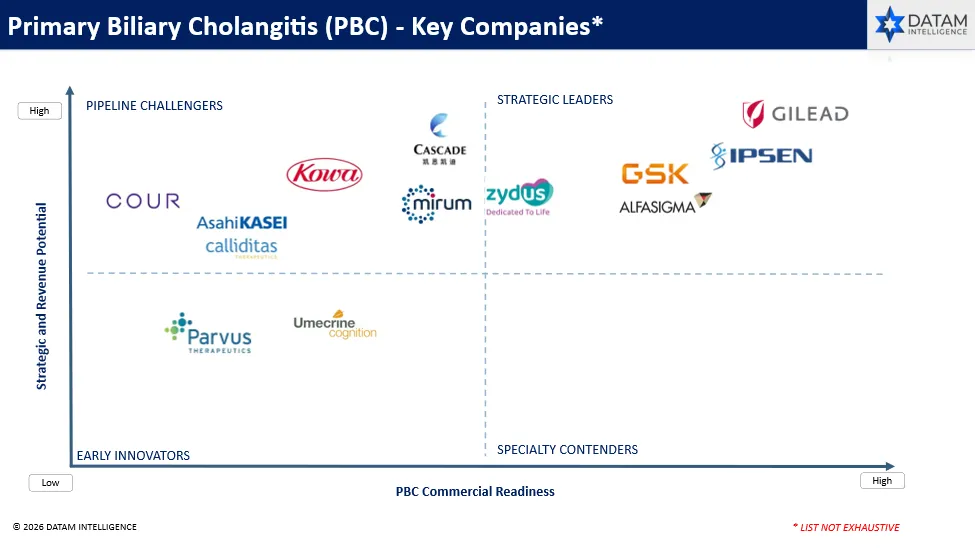
- Gilead, Ipsen and GSK- Alfasigma hold leading positions through LIVDELZI, IQIRVO and LYNAVOY, supported by approved products, specialist relationships and established commercialization capabilities.
- Zydus is approaching commercialization readiness with saroglitazar, potentially intensifying competition around biochemical response, tolerability, dosing convenience and positioning within the second-line treatment pathway.
- Cascade, Kowa, Mirum, COUR and Calliditas-Asahi Kasei are pursuing differentiated approaches spanning PPAR modulation, pruritus management, immune tolerance and antifibrotic activity. Clinical validation and development timelines will determine their competitive impact.
- Parvus and Umecrine remain at earlier development stages but could address important treatment gaps through antigen-specific immune modulation and therapies targeting cognitive dysfunction and fatigue.
- Future market positioning will depend on durable biochemical normalization, meaningful symptom relief, favorable hepatic safety, fibrosis control and evidence of reduced clinical progression. Companies combining differentiated outcomes with convenient administration, clear patient segmentation and compelling payer evidence will be best positioned to capture market share.
Target Opportunity Profile (TOP)
To compete effectively with ursodiol and newer PBC therapies, emerging candidates must demonstrate differentiated biochemical control, favorable long-term safety, clinically meaningful symptom improvement and potential to reduce progression toward cirrhosis and liver-related complications.
Target Opportunity Profile (TOP) - Competitive Attributes
| Dimension | Desired Profile for Emerging PBC Therapies | Strategic Rationale |
| Safety |
| PBC requires lifelong therapy; predictable hepatic safety and tolerability are essential for sustained treatment adherence. |
| Efficacy |
| Biochemical response is the principal regulatory and clinical benchmark, but long-term differentiation requires evidence of improved clinical outcomes. |
| Mechanism of Action |
| Novel mechanisms may address heterogeneous disease biology and provide alternatives for patients inadequately controlled by existing therapies. |
| Route of Administration |
| Convenient delivery can improve adherence and reduce disruption to established hepatology-care pathways. |
| Dosing Frequency |
| Lower treatment burden supports persistence, particularly because PBC therapy is typically continued indefinitely. |
| Modality |
| Multiple modalities enable intervention across bile-acid regulation, inflammation, fibrosis, autoimmunity and symptom pathways. |
| Durability |
| Durable control is critical for reducing cumulative liver injury and delaying cirrhosis, decompensation and transplantation. |
| Innovation Level |
| Mechanistic and biomarker differentiation can support premium positioning and more targeted treatment selection. |
| Clinical Impact |
| Clinicians and payers increasingly require benefits extending beyond surrogate biochemical improvements. |
Patient-Population Targeting |
| Phenotype-specific positioning can concentrate clinical benefit and support clearer treatment-selection pathways. |
| Treatment Positioning |
| Flexible positioning can expand the addressable population and support integration across different lines of therapy. |
| Commercial Differentiation |
| Market uptake will depend on clinically meaningful differentiation, manageable treatment costs and seamless integration into specialist practice. |
Unmet Needs & Market Dynamics
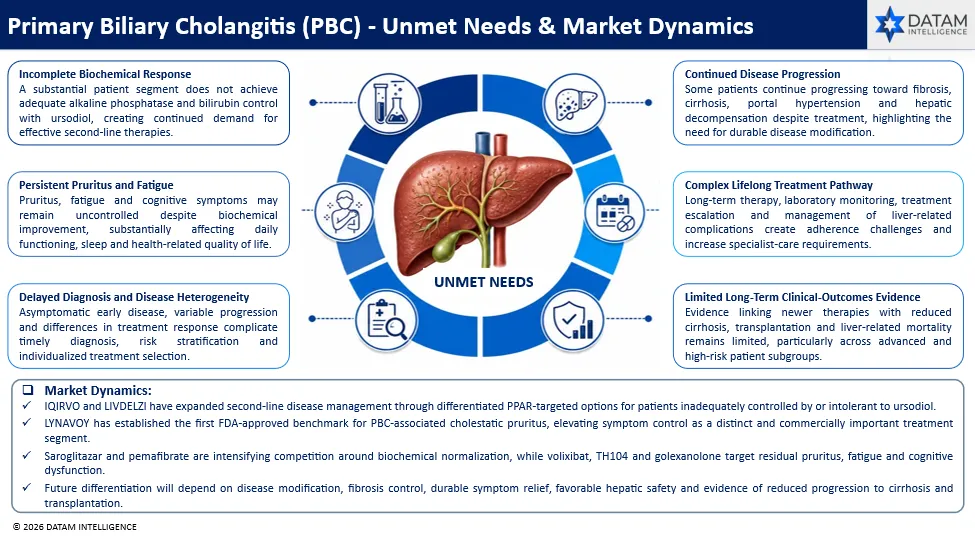
Primary biliary cholangitis presents substantial unmet need because existing therapies primarily improve cholestatic biochemical markers but do not consistently prevent fibrosis, cirrhosis or liver-related complications. Many patients remain inadequately controlled by ursodiol, while pruritus, fatigue and cognitive symptoms may persist despite biochemical improvement. The treatment landscape is evolving toward earlier diagnosis, risk-based treatment escalation, symptom-specific management and novel mechanisms targeting inflammation, fibrosis and underlying autoimmunity. Future differentiation will depend on durable biochemical normalization, meaningful symptom relief, favorable long-term hepatic safety and evidence demonstrating reduced progression to cirrhosis, hepatic decompensation, liver transplantation and liver-related mortality.
Strategic Summary
- The PBC competitive landscape is shifting from an ursodiol-dominated treatment pathway toward a segmented market encompassing biochemical control, symptom management and disease modification. IQIRVO and LIVDELZI have strengthened second-line treatment for patients with an inadequate response to ursodiol, while LYNAVOY establishes a dedicated option for cholestatic pruritus. Consequently, pipeline assets must compete against increasingly indication-specific clinical benchmarks.
- Biochemical improvement, particularly reductions in alkaline phosphatase and bilirubin, will remain essential but is unlikely to provide sustainable differentiation independently. Competitive advantage will require evidence that biochemical responses translate into fibrosis control, delayed hepatic decompensation, reduced transplantation risk and improved transplant-free survival.
- Persistent pruritus, fatigue and cognitive impairment remain commercially important opportunities because biochemical responders may continue to experience substantial symptom burden. Assets capable of delivering durable, patient-relevant improvement without compromising hepatic safety could secure differentiated positioning alongside disease-modifying treatment.
- Commercial success will ultimately depend on an integrated value proposition combining durable efficacy, symptom relief, hepatic safety, convenient oral administration and limited monitoring requirements. Strong responder identification, compatibility with ursodiol, credible long-term evidence and demonstrable reduction in downstream clinical burden will be central to specialist adoption, payer acceptance and sustained market access.
Why Buy Our Primary Biliary Cholangitis (PBC) Competitive Intelligence Report?
The PBC market is entering a more competitive treatment era, driven by the approvals of IQIRVO, LIVDELZI and LYNAVOY, regulatory advancement of saroglitazar and growing demand for therapies that deliver biochemical control, symptom relief and durable protection against liver-disease progression. As treatment pathways expand beyond ursodiol, companies require clear intelligence on clinical differentiation, treatment sequencing, patient risk profiles, regulatory progress, access dynamics and pipeline disruption. Our report translates the evolving PBC landscape into actionable clinical, commercial and investment strategies.
Identify Where Competition Is Intensifying
Understand how IQIRVO and LIVDELZI are reshaping second-line disease management, how LYNAVOY is establishing a distinct pruritus-treatment segment and which pipeline mechanisms may drive the next competitive wave.
Prioritize the Right Patient Segments
Assess commercially relevant populations, including inadequate ursodiol responders, ursodiol-intolerant patients, patients with persistent biochemical elevation, compensated cirrhosis and clinically significant pruritus or fatigue.
Evaluate Asset Differentiation
Compare therapies based on alkaline phosphatase and bilirubin response, symptom improvement, fibrosis control, hepatic safety, dosing frequency, treatment durability and compatibility with established PBC-treatment pathways.
Track Regulatory and Launch Readiness
Monitor clinical readouts, FDA review milestones, approval timelines, confirmatory studies, label-expansion opportunities, geographic access developments and commercialization readiness across approved and investigational therapies.
Support Pricing and Access Planning
Understand payer expectations, reimbursement barriers, treatment eligibility, laboratory-monitoring requirements, treatment sequencing and evidence thresholds influencing specialist adoption across major markets.
Strengthen Business Development Decisions
Identify licensing, partnership, acquisition and investment opportunities across PPAR agonists, FXR agonists, IBAT inhibitors, antifibrotic agents, tolerogenic nanoparticles and antigen-specific immune-modulation platforms.
